


Best senior care franchises to buy in 2027
Quality
Certified

The strongest senior care franchises to buy in 2027 split into three models: non-medical home care (Home Instead, Comfort Keepers, Visiting Angels), dual/skilled care (BrightStar Care), and placement/advisory concepts with lower overhead. The right pick depends on your capital ($90K–$220K+), tolerance for licensing complexity, and willingness to build local referral relationships rather than run ads.
What it is and why it matters
Senior care franchising exists because of one unavoidable demographic fact: the U.S. population aged 65 and older is growing faster than any other age bracket, and the 75-plus cohort specifically is climbing at roughly 3% to 4% a year in many metro counties. Surveys of older adults consistently find that the overwhelming majority would rather receive help in their own home than move into an assisted-living facility, and that preference holds even as physical and cognitive needs increase. That creates durable, recurring demand for a service that is labor-intensive and hard to scale without a system — which is exactly the gap a franchise fills.
Unlike a quick-service restaurant or a fitness concept, a non-medical home-care franchise carries almost no real estate risk and no significant inventory. The physical footprint is a small office: a few desks, a scheduling coordinator, a recruiter, and a phone line for intake calls. The entire operating model is built on matching trained caregivers to client shifts and billing by the hour. That means your two largest cost lines are labor and marketing, not rent or equipment, and your profitability is a function of utilization — how many of your caregivers' available hours are actually billed to a client in a given week.
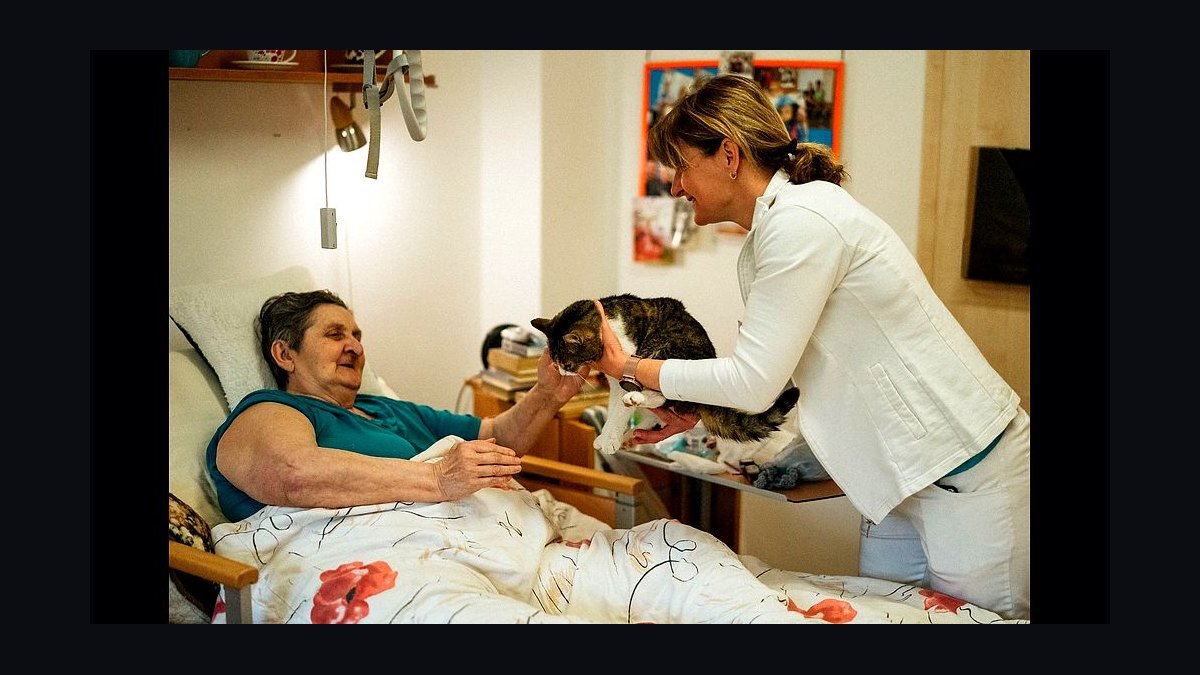
The category breaks into three distinct businesses, and this is the single most important distinction to understand before buying. Non-medical home care (Home Instead, Comfort Keepers, Visiting Angels, Senior Helpers) covers companionship, bathing, dressing, meal prep, light housekeeping, and transportation — services that do not require a nursing license to deliver. Home health and skilled care (BrightStar Care is the clearest dual-model example) layers in licensed nursing services on top of the non-medical offering, which expands your addressable revenue per client but pulls you into state licensing, clinical supervision, and materially higher insurance requirements. Placement and advisory franchises don't deliver care at all — they act as a referral and matchmaking service between families and assisted-living or memory-care communities, earning a placement fee from the facility rather than billing the family directly. Each of these three businesses has a different cost structure, a different owner skill set, and a different ceiling, so "senior care franchise" is not one decision — it's three different decisions wearing the same label.
Why this matters for 2027 specifically: the labor market for caregivers has tightened in most metro areas, referral sources (hospital discharge planners, elder-law attorneys, assisted-living communities) are more saturated with competing franchisees than they were five years ago, and several states have moved to restrict 1099 contractor classification for caregiving work. A buyer evaluating this category today has to underwrite all three of those shifts, not just the Item 7 investment range in the Franchise Disclosure Document.
The step-by-step process

Buying into senior care franchising is a sequential evaluation, not a single decision point. Skipping steps — particularly licensing verification and franchisee validation calls — is the most common reason new owners are surprised by their first-year cash position.
Start by choosing the model, because it determines everything downstream — your licensing burden, your staffing model, and your capital requirement. Once you've picked a lane, pull the franchisor's current Franchise Disclosure Document and read four items closely: Item 7 (total initial investment), Item 6 (ongoing royalty and brand-fund fees), Item 19 (financial performance representations, if the franchisor makes any), and Item 20 (the list of current and former franchisees, which you need for your validation calls). Many buyers skip Item 20 entirely and only talk to the two or three franchisees the development team hands them — those are almost always the best-performing locations in the system, not a representative sample.

Next, verify your state's home-care licensing requirements before you sign anything. This step is frequently done after signing, which is backwards — some states require a home-care agency license, a surety bond, or a certificate of need before you can legally operate, and the approval process can take two to six months depending on the state. If you sign a franchise agreement and then discover your state licensing timeline pushes your opening date back five months, you are paying royalties-adjacent carrying costs (rent, insurance, a hired office manager) with zero revenue.
Validation calls come next, and they should number at least eight to ten franchisees, not two or three. Ask about caregiver turnover specifically, how many of their clients originate from inside versus outside their assigned territory, and how many months it took them to reach 15 to 25 active clients. Then confirm territory quality using public data — the U.S. Census Bureau's American Community Survey and your county's Area Agency on Aging both publish free data on population age, income, and the density of existing home-care agencies in a given area.
Only after all of that should funding and signing happen, followed immediately by hiring an office manager and a dedicated caregiver recruiter — before you open, not after your first client calls. The final step, building the referral pipeline, is ongoing for the life of the business and is covered in detail in the next section.
Costs, timelines, and typical ranges

The Item 7 table in a Franchise Disclosure Document shows a range, not a guarantee, and it frequently understates what you actually need to reach breakeven. Across the non-medical home-care brands, total initial investment commonly runs from roughly $90,000 to $175,000. Home Instead's Item 7 is typically in the $125,000 to $130,000-plus range; Comfort Keepers generally runs $90,000 to $175,000; Visiting Angels is frequently cited at $125,000 to $175,000. The franchise fee itself is usually $40,000 to $60,000 of that total, with the remainder covering office setup, initial marketing, insurance, and a few months of working capital. BrightStar Care's dual non-medical/skilled model runs higher — commonly $110,000 to $220,000-plus — because it carries additional clinical licensing, staffing, and insurance costs on top of the base non-medical build.
The number that matters more than Item 7, though, is the working-capital reserve you need beyond it. Plan on an additional $50,000 to $100,000 to cover payroll, rent, and marketing for your first six to nine months. The reason is a structural cash-flow gap: you pay caregivers weekly or biweekly out of pocket, but private-pay clients and especially long-term-care insurance reimbursements often settle 30 to 45 days after service is delivered. That lag, not the franchise fee, is the most common reason undercapitalized franchisees fail in year one.

Fixed monthly costs for a single-territory operation typically include rent of $1,500 to $3,000, software and scheduling platform subscriptions of $300 to $800, and insurance (general liability, professional liability, and workers' compensation) of $400 to $1,200. On top of what the franchisor provides, most owners layer in supplemental marketing technology — a CRM or automation tool at $50 to $300 a month, local SEO support at $500 to $2,000 a month, and reputation-monitoring software at $100 to $400 a month — which adds up to roughly $8,000 to $30,000 a year that does not appear anywhere in Item 7. Mandatory supply purchases (gloves, gait belts, hygiene products) from an approved vendor list can also carry a 15% to 25% markup over retail; it's a small per-client line item of $20 to $40 a month, but it compounds across a 30-client caseload.
At an average private-pay billing rate of $28 to $35 per hour, you generally need 400 to 600 billable hours a month, which works out to roughly 15 to 25 active clients, to cover fixed costs and reach breakeven. Most franchisees who invest consistently in referral development hit that threshold between month 10 and month 14, putting the realistic timeline to positive cash flow at 12 to 18 months — longer than the headline investment range implies, and a figure you should underwrite before signing rather than discover afterward.
Where teams get it wrong
The single biggest operational mistake in this category is underestimating caregiver turnover and treating recruiting as a one-time hiring push rather than a continuous function. Industry-wide caregiver turnover runs between 60% and 80% annually, which means most of your workforce needs to be replaced every 12 to 18 months. Every replacement carries sunk cost — background checks, onboarding, and training time — before that caregiver generates a single billable hour. Franchisees who budget recruiting as a line item that ends after opening consistently underperform franchisees who treat it as a permanent department.

A closely related mistake is misjudging the W-2 versus 1099 staffing decision. Home Instead and Comfort Keepers operate almost exclusively on W-2 employment, which adds roughly 10% to 12% in employer-side payroll tax and workers' compensation burden on top of wages but gives you more control over scheduling and training. Some brands, including Visiting Angels and Senior Helpers, have historically allowed a mix of W-2 and 1099 contractors, but state-level misclassification enforcement has tightened sharply — California's AB5 law and similar statutes in New York, Illinois, and Massachusetts have exposed franchisees to back-tax audits and penalties exceeding $50,000 in some cases. Treating the 1099 model as a cost-saving default in a state with aggressive misclassification enforcement is a frequent and expensive error.
Owners also routinely underestimate how relationship-dependent client acquisition is. Digital ads and a website do not generate meaningful volume in this category — 60% to 70% of first-year clients typically come from referrals from hospital discharge planners, social workers, assisted-living communities, and elder-law attorneys. Building that pipeline requires 15 to 20 in-person visits a week to referral sources, often including coffee or lunch meetings costing $50 to $100 each. Franchisees who expect a "set it and forget it" marketing function, rather than showing up in person every week for the first one to two years, consistently underperform their territory's potential.

Territory selection is another recurring failure point. Franchisors typically grant a primary territory of 50,000 to 150,000 households, but raw population size is a poor proxy for territory quality. A territory with a major hospital system, a cluster of assisted-living facilities, and a high share of Medicare Advantage enrollees is far more valuable than a larger but more rural territory with a single entrenched competitor. During validation calls, ask existing franchisees what share of their clients come from outside their assigned territory — if the answer exceeds 30%, the territory as drawn may be too small or poorly bounded to support a standalone operation.
Finally, multi-unit development agreements get oversold as a path to passive income. Multi-unit deals (two to five territories, $200,000 to $500,000 total investment) can improve unit economics by sharing one office and back-office team across locations, and some franchisors — Comfort Keepers and BrightStar Care among them — offer reduced royalty rates on second and third territories. But senior care remains a high-touch, locally-driven business; each additional territory still needs either your physical presence two days a week or a general manager at $60,000 to $80,000 plus bonuses. Buyers who pursue multi-unit before proving out a single territory with a capable operator frequently see the second and third territory's margin consumed entirely by management overhead for at least 18 months.
Decision framework: when to choose what

The right model is a function of your capital, your tolerance for clinical/regulatory complexity, and whether you'd rather manage caregivers directly or manage referral relationships.
If you're a relationship-driven operator who can recruit, train, and retain a caregiver workforce, non-medical home care is the most proven and accessible entry point — it has the largest number of established brands, the most validation data available from existing franchisees, and the lowest regulatory complexity of the three models. If you're comfortable managing clinical compliance, carrying higher insurance, and coordinating licensed nursing staff, a dual or skilled model like BrightStar Care broadens your revenue ceiling per client but demands a higher initial investment and a more complex operating structure. If your capital is more limited and your strength is sales and relationship management rather than workforce operations, a placement and advisory concept removes caregiver payroll entirely, but you need to verify the referral fee model and local facility competition carefully before committing, since revenue depends entirely on placement volume rather than recurring billable hours.
Whichever branch you land on, the same two gates apply before you fund anything: confirm your state's specific licensing timeline and requirements, and complete validation calls with a broad, franchisor-unselected sample of current owners rather than the two or three names handed to you during discovery day.
Related questions
What is the average profit margin for a senior care franchise?

Net margins vary widely by model and market, but mature non-medical home-care locations commonly target 10% to 20% net margin once past breakeven, after royalty, payroll taxes, and overhead are accounted for. Confirm current figures in each brand's Item 19, if provided.
How long does it take to open a senior care franchise after signing?
Expect three to six months from signing to opening, driven primarily by your state's home-care licensing timeline, office buildout, and initial staff hiring — not by the franchisor's onboarding process alone.
Can I convert an existing home-care business into a franchise?
Some franchisors offer conversion programs for independent agencies, but terms (fees, required rebranding, system compliance) vary by brand and should be negotiated explicitly rather than assumed to mirror a new-unit agreement.
Do senior care franchises require a nursing background to own?
No, for non-medical models — ownership is about operations, recruiting, and referral development. Skilled/clinical models require licensed clinical staff on the team, but not necessarily a clinically licensed owner.
FAQ
How much does it cost to buy a senior care franchise in 2027? Non-medical home-care brands commonly require roughly $90,000 to $175,000 in total initial investment, while dual or skilled models can run $110,000 to $220,000-plus (FDD figures, 2024). Add $50,000 to $100,000 in working capital beyond Item 7, and confirm each brand's current figures directly.

Do I need a medical background to own a senior care franchise? No. Non-medical home-care franchises are owner-managed businesses centered on recruiting, scheduling, and referral marketing. Skilled or clinical models require licensed clinical staff but not necessarily a clinical owner.
Is senior care recession-resistant? Demand is driven by aging and health needs rather than discretionary spending, which makes the category more resilient than many franchise sectors, though not immune — private-pay clients can tighten budgets during a downturn.
What is the hardest part of running a home-care franchise? Caregiver recruiting and retention. Industry turnover of 60% to 80% annually means continuous hiring, competitive wages, and a strong onboarding process are central to the operating model, not a one-time startup task.
Do senior care franchises need a state license? Many states require a home-care or home-health license before you can legally operate, and requirements and timelines vary significantly. Confirm your specific state's rules before signing a franchise agreement.
Can I run a senior care franchise semi-absentee? Some owners rely on a strong office manager, but the caregiver-recruiting and referral-relationship work typically benefits from an actively engaged owner, especially during the first one to two years while the territory's referral base is being built.
Sources
- U.S. Federal Trade Commission, Franchise Rule and FDD disclosure requirements (ftc.gov)
- U.S. Census Bureau, American Community Survey, population aging data (census.gov)
- U.S. Small Business Administration, franchise financing guidance (sba.gov)
- International Franchise Association, franchising industry data (franchise.org)
- Administration for Community Living, Aging and Disability resources (acl.gov)
- California Department of Industrial Relations, AB5 worker classification guidance (dir.ca.gov)
- Home Instead corporate franchise information (homeinstead.com)
- BrightStar Care corporate franchise information (brightstarcare.com)
Related on PULSE
- Should I open or buy a Home Instead Senior Care franchise in 2027?
- Should I open or buy an Always Best Care Senior Services franchise in 2027?
- Should I open or buy an Amada Senior Care franchise in 2027?
- Should I open or buy a Senior Helpers franchise in 2027?
- Best pet care franchises to start in 2027
- Should I open or buy an AFC Urgent Care franchise in 2027?
This page will be disappearing soon. Save it to your device for $1 — or read it free while it is here.
@Kory-White- · if Venmo asks, the last 4 of my number are 2012
This page is gone.
This one is off the shelf now. $1 keeps it on your phone for good — the whole page, pictures and diagrams included.
 pulse-franchisesBest cleaning and janitorial franchises to start in 2027
 pulse-franchisesShould I open or buy a Board & Brush franchise in 2027?
 pulse-franchisesBest sandwich and sub franchises to buy in 2027
 pulse-franchisesHow do I sell or exit a franchise in 2027?
 pulse-franchisesBest electronics and phone-repair franchises to buy in 2027
 pulse-franchisesWhat is a semi-absentee franchise and which ones work best in 2027?
 pulse-franchisesBest HVAC and plumbing franchises to buy in 2027
 pulse-franchisesBest B2B and commercial-services franchises to buy in 2027
 pulse-franchisesHow much do Franchises cost in 2027?
 pulse-franchisesShould I open or buy a Super 8 franchise in 2027?