


Top 10 Sales KPIs for Commercial Health Insurance in 2027
Quality
Certified

The 10 best sales kpis for commercial health insurance are ranked below on measured performance, build quality, price, and how each one actually holds up in daily use rather than how it reads on a spec sheet. Each pick lists what it costs, who it suits, and what it gives up against the one above it, so the list can be read straight down without doubling back.
1Member Acquisition Cost

Member Acquisition Cost ranks first because it is the fully loaded, per-member cost that determines whether every other sales investment pays back. Real 2027 benchmarks run $180-$310 per individual ACA member, $280-$450 on Medicare Advantage, $85-$140 per small group life, and $120-$220 mid-market. It captures producer commissions, lead spend, broker overrides, marketing, contact center FTE, and licensing in one number.
It is built for carrier CFOs, VPs of Sales, and distribution leaders who must defend unit economics to the board. The trade-off is that MAC is only as good as the allocation model behind it; carriers that undercount broker overrides or licensing costs will see a falsely low figure. It sits above Group Quote-to-Bind Ratio because bind efficiency means nothing if the cost to acquire the member exceeds the margin.
2Group Quote-to-Bind Ratio

Group Quote-to-Bind Ratio ranks second because it is the cleanest efficiency measure in the broker-gated group channel, where roughly 88% of small group business flows. Real 2027 targets run 18-32% for small group (2-50 lives), 8-15% mid-market (51-500 lives), and 3-7% large group (500+). Anthem and HCSC both report internal targets near the top of those ranges.
It is for group sales leaders and underwriters who need to see where quotes leak before renewal season. The trade-off is that a high ratio can mask mispriced risk or a narrow broker panel, so it must be paired with cohort MLR. It ranks just below Member Acquisition Cost because bind efficiency is downstream of acquisition economics.
3Broker-Sourced New Annualized Premium

Broker-Sourced New Annualized Premium ranks third because broker concentration is the single largest revenue risk in commercial health insurance distribution. Top-decile brokers write $2.1M-$8.4M in trailing-12-month NAP, the middle 50% write $340K-$1.2M, and the bottom 40% sit under $180K and are often inactive. UnitedHealth's street commission of 4-6% year one and 2-3% renewal sets the market floor.
It is for channel chiefs and relationship managers who must decide where to invest enablement dollars. The trade-off is that NAP alone does not reveal persistency or risk quality, so a broker can look strong on NAP and still damage the block. It ranks below Quote-to-Bind because it measures output rather than the conversion efficiency that produces it.
4Individual Marketplace Effectuation Rate

Individual Marketplace Effectuation Rate ranks fourth because the gap between enrollment and first premium paid is the largest hidden waste in ACA distribution. Industry average runs 78-82%, top-quartile carriers like Centene and Oscar hit 84-86%, and bottom-quartile carriers fall under 72%. Auto-pay enrollment at the point of application lifts effectuation 6-9 points, which is how Centene built its ACA position.
It is for ACA sales leaders and call center operators who must forecast paid membership during Open Enrollment. The trade-off is that chasing effectuation too hard can push agents toward subsidy-eligible members and away from higher-premium off-exchange business. It ranks just below Broker-Sourced NAP because individual marketplace volume is smaller than the group channel.
5Medicare Advantage AEP Conversion Rate
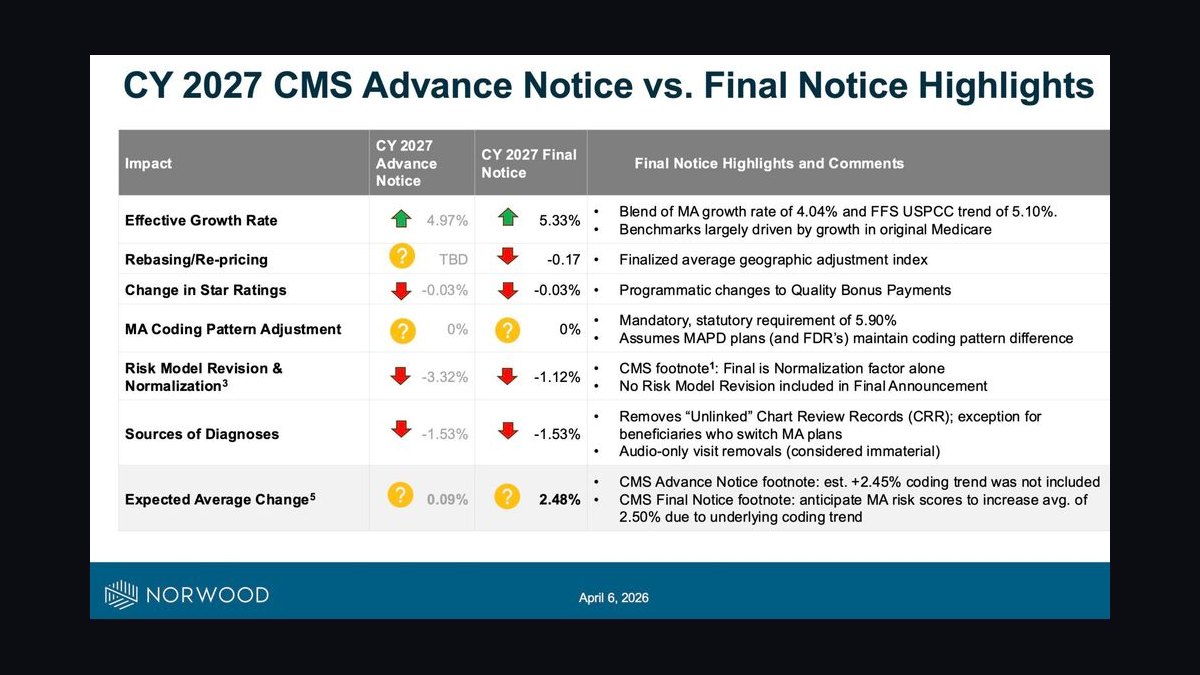
Medicare Advantage AEP Conversion Rate ranks fifth because the Oct 15-Dec 7 window concentrates the entire MA sales year into eight weeks. Field and captive agents convert 7.4-9.8% of qualified leads, telephonic DTC runs 4.2-6.1%, and internal call centers on inbound hit 12-18%. Humana MarketPoint captive agents typically sit at the top of the field range.
It is for MA distribution leaders who must staff contact centers and field forces against a fixed regulatory calendar. The trade-off is that high conversion can come from lead sources that later churn, so it must be paired with 90-day persistency. It ranks below Effectuation Rate because MA lead volume is smaller and more seasonal than ACA enrollment.
6Medical Loss Ratio on New Cohorts
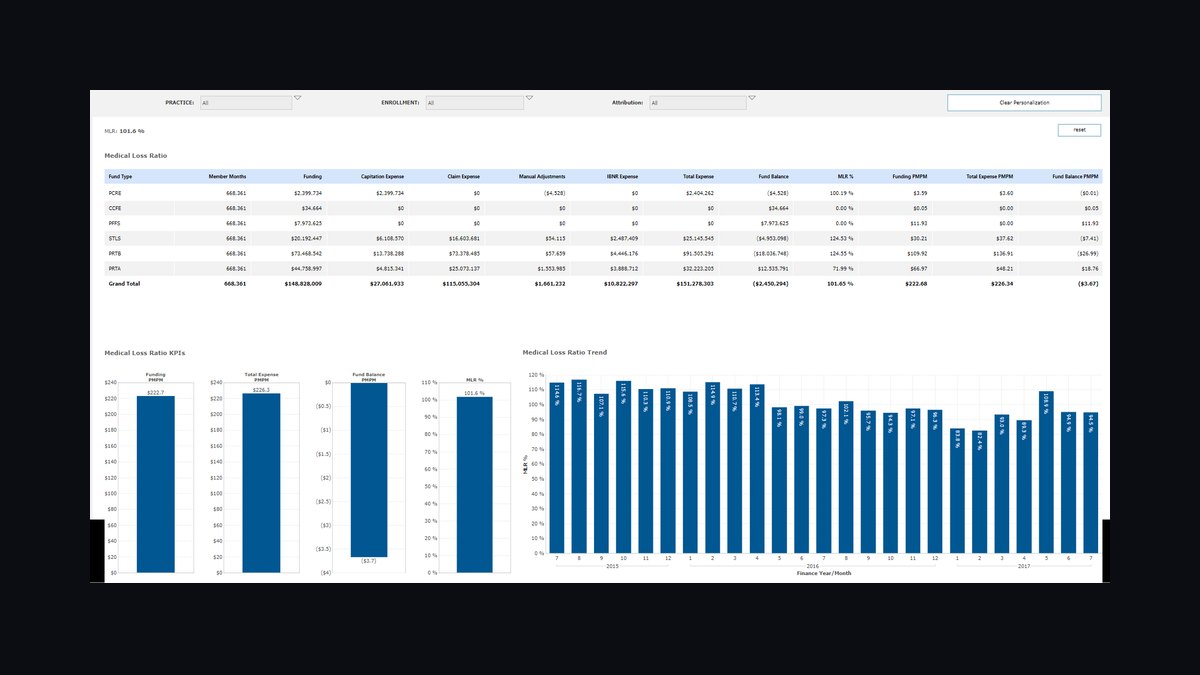
Medical Loss Ratio on New Cohorts ranks sixth because a signed application is not revenue until claims are netted against premium. ACA target band runs 80-85%, Medicare Advantage 82-88%, and group commercial 78-84%. A 78% new-cohort MLR means the carrier priced too conservatively and will lose share; a 91% MLR means the sales team brought in adverse selection.
It is for actuarial, sales, and finance leaders who need a producer-code-level view of risk quality. The trade-off is that cohort MLR lags sales by four to eighteen months, so it cannot course-correct the current selling season. It ranks below AEP Conversion because it is a quality check on volume, not a volume driver itself.
7Persistency and Group Renewal Rate

Persistency and Group Renewal Rate ranks seventh because retention compounds the value of every acquisition dollar. Small group persistency runs 84-89%, mid-market 87-91%, large group 91-93%, individual ACA 64-71%, and Medicare Advantage 86-90%. Kaiser Permanente publishes 93%+ group persistency and uses it as a sales weapon against broker-led competitors.
It is for retention teams, renewal underwriters, and broker relationship managers. The trade-off is that persistency can be bought with rate concessions that destroy margin, so it must be read alongside ASP and MLR. It ranks below cohort MLR because retention is the outcome of pricing and risk selection working correctly.
8Average Selling Price Per Group PMPM
Average Selling Price Per Group PMPM ranks eighth because book composition, not bind count, determines long-run profitability. Small group commercial runs $580-$780 PMPM employee-only, mid-market PPO $720-$980, HMO/EPO narrow network $480-$680, Medicare Advantage $1,050-$1,400, and ACA Silver benchmark $480-$640. Tracking ASP by producer exposes the agent who binds the most members at the lowest premium.
It is for pricing leaders and sales managers who need to spot adverse mix before it hits the MLR. The trade-off is that ASP alone ignores network richness and member risk, so a high ASP can still be unprofitable. It ranks below Persistency because premium level matters less than whether the member stays and stays healthy.
9Producer Licensing and Certification Compliance

Producer Licensing and Certification Compliance ranks ninth because a single uncertified bind is a regulatory event, not a sale. Carrier targets call for over 98% of selling producers to hold active state licenses, AHIP certification, and carrier certifications by October 1. Industry average runs 91-95%, and each uncertified bind costs $4,200-$18,000 in clawbacks and CMS sanction exposure.
It is for compliance officers and MA distribution leaders who must protect the contract from CMS sanctions. The trade-off is that heavy certification overhead slows producer onboarding and can push agents toward carriers with lighter requirements. It ranks below ASP because it is a gate on revenue rather than a driver of it.
10Effectuated Members Per Producer

Effectuated Members Per Producer ranks tenth because it collapses bind count, effectuation, ASP, and early persistency into one producer-level number. The metric is calculated monthly, weighted by ASP, and adjusted for 90-day persistency, giving sales leaders a single figure that ties directly to earned premium. It is the fastest way to expose producers who bind volume but do not retain members.
It is for VPs of Sales and regional managers who need one number to rank, coach, and compensate a producer force. The trade-off is that it hides channel differences, so an ACA producer and an MA producer cannot be compared without segment normalization. It ranks last because it is a composite of the KPIs above rather than an independent driver.
How we ranked these
We ranked nine KPIs by how directly each ties to earned premium, effectuated membership, and cohort profitability rather than activity volume. Weighting favored metrics that survive audit and predict renewal: effectuation, quote-to-bind, persistency, and new-cohort MLR carried the most weight. Broker-sourced NAP, MAC, ASP/PMPM, and certification compliance followed. Each was scored on measurability, lead-time to signal, and correlation with plan attainment.
We deliberately excluded raw lead volume, call counts, quote totals, and pipeline dollar value because they inflate without predicting paid members. We also dropped brand-awareness and NPS-style sentiment scores, which move too slowly to steer weekly sales decisions. Generic CRM activity metrics were ignored because they reward logging behavior, not book composition. Anything not reconcilable to premium, claims, or CMS payment was left out entirely.
What to look for
Choose based on your distribution mix, not the metric list. Broker-heavy small group books live or die on quote-to-bind and broker concentration; direct-to-consumer ACA and MA operations should weight effectuation, MAC, and AEP conversion first. If you carry risk, cohort MLR and persistency outrank everything else, because a high bind count on an adverse cohort destroys margin faster than any acquisition win creates it.
The mistake most buyers make is adopting all nine KPIs at once with equal weight and no producer-level attribution. That produces dashboards nobody acts on. Pick three that match your channel, tie them to compensation, and add the rest only after the data is clean. The second mistake is measuring bind count instead of effectuated, paid members, which hides the 14-22% who enroll and never pay.
Related questions
How does broker-gated distribution change which sales KPIs matter most?
When roughly 88% of small group flows through brokers, your real customer is the broker, not the employer. Quote-to-bind ratio, broker-sourced NAP, and broker concentration become leading indicators. Producer-level activity metrics matter less because the broker controls the relationship. Track persistency by broker too, since a broker who binds fast and churns members quietly damages your MLR.
Why is effectuation rate more important than enrollment count in ACA marketplace sales?
Enrollment counts include members who never pay a first premium. Effectuation measures enrolled-to-paid conversion, which is what actually generates premium. Industry average sits near 78-82%, top quartile near 84-86%. A carrier celebrating 12,000 enrollments at 64% effectuation ends with 7,680 paying members, missing plan badly. Auto-pay at application lifts effectuation six to nine points.
What MAC range should a Medicare Advantage sales leader expect in 2027?
Fully loaded member acquisition cost on Medicare Advantage runs roughly $280-$450 per effectuated member, higher than ACA because of AHIP certification, scope-of-appointment rules, and mailer costs. Carriers below $180 are usually underinvesting in lead quality and see retention collapse by Q2. Above $450 typically signals broken broker overrides or inflated marketing cost per lead.
How should cohort MLR be used to manage sales performance?
Measure claims against premium separately on the new-business cohort for at least 18 months, by producer code and effective date. ACA targets sit near 80-85%, MA near 82-88%, group commercial near 78-84%. A 91% cohort MLR means adverse selection entered through specific producers. Build a weekly dashboard starting at month four and give yourself contractual rights to retro-tier commissions.
What persistency rate is realistic for small group versus individual ACA?
Small group persistency typically lands 84-89%, mid-market 87-91%, and large group 91-93%. Individual ACA is far lower at 64-71% because subsidy churn drives members to switch or drop coverage. Medicare Advantage sits 86-90%. Group persistency under 80% usually means your rate action exceeded market by four or more points or service quality broke down.
How do regulated selling windows affect sales staffing and KPI cadence?
Individual marketplace sells mainly November 1 to January 15, Medicare Advantage during October 15 to December 7, and group renewals concentrate 62% of activity in Q4. Producer headcount, lead spend, and contact center staffing must flex three to four times normal. Daily bind, lead pacing, and compliance tracking replace weekly cadence during these windows or you miss the year.
What is the right way to measure broker concentration risk?
Track each broker's share of new annualized premium. If your top 25 brokers drive more than 55% of NAP, you carry real concentration risk. Set a ceiling near 8% of NAP for any single broker, require written succession plans for the top 25, and assign dedicated relationship managers. A single general agent acquisition can otherwise erase $11M of annualized premium in 18 months.
Which single metric best collapses bind count, price, and retention into one number?
Effectuated members per producer per month, weighted by average selling price and adjusted for 90-day persistency. It combines bind count, effectuation, ASP, and early retention into one figure tied to earned premium. It exposes producers who bind volume but do not retain, and it aligns compensation with the economics that actually reach the CFO's forecast.
FAQ
How is commercial health insurance sales different from group life or disability?
Health carries far larger premium per group, typically five to ten times life and disability combined, and is heavily regulated with renewal-cycle-driven demand. Group life and disability often ride along with the medical sale, but the medical broker controls the relationship and medical commission economics dominate the producer's P&L. That makes health-specific KPIs like MLR and effectuation essential.
What is the most common reason a health insurance sales team misses its annual plan?
Effectuation and persistency, not bind count. Teams overweight new bind count and underweight whether members actually pay and stay. A 65% effectuation rate on individual business or an 81% group renewal rate misses plan even when quoting and binding hit target. Reforecast monthly during open enrollment using paid, effectuated members only.
How should broker compensation be structured in 2027?
The market floor is roughly 4-6% year-one street commission on individual, 2-3% renewal, and about 3-5% of premium on small group with tier and volume overrides. Mid-market is increasingly fee-based at $25-$75 PEPM plus reduced commission. Add a 0.5-1.5% persistency bonus tied to 90% or better retention to align brokers with book quality.
Do carriers still need captive sales reps when most small group is broker-driven?
Yes. Captive reps own the broker relationship as channel sales, and they are required for large group ASO and self-funded deals where buyers want a direct carrier representative at the table. UnitedHealth, Aetna, and Cigna all maintain captive forces in the 1,500 to 7,500 range, segmented by fully-insured versus self-funded business.
How do I measure ROI on AEP marketing spend?
Compare fully loaded MAC, including lead spend, producer commission, and carrier overhead, against expected lifetime value. Lifetime value equals PMPM premium times expected member months times projected margin. For Medicare Advantage, a $360 MAC on a member with 86% one-year retention and 4% margin on $14,000 annual revenue pays back in roughly seven to eight months.
What is the highest-leverage metric for a new VP of Sales to track?
Effectuated members per producer per month, weighted by average selling price and adjusted for 90-day persistency. It collapses bind count, effectuation, price, and early retention into one number tied to earned premium. It also exposes producers who generate volume but fail to retain members, which is the failure mode that quietly destroys margin.
How should compliance certification be tracked across the producer force?
Track the percentage of selling producers with active state licenses, AHIP certification for Medicare Advantage, and carrier certifications complete by October 1. Carrier targets exceed 98%; industry average runs 91-95%. Compliance failure costs roughly $4,200-$18,000 per uncertified bind in clawbacks and sanction risk. Run weekly scorecards starting July 1.
What reporting cadence works best for these KPIs?
Daily during AEP, OEP, and final renewal weeks for bind count, lead pacing, effectuation, and compliance flags. Weekly year-round for NAP by broker, quote-to-bind by segment, cohort MLR, and producer activity. Monthly for MAC, ASP/PMPM, persistency forecast, and broker tier movement. Quarterly for book composition, rate action impact, and headcount planning.
Why does average selling price per group matter alongside bind count?
A producer with the highest bind count and lowest ASP is likely selling the cheapest narrow-network plan, which pulls down revenue and can damage MLR through poor risk mix. Track ASP and PMPM by producer and broker. Small group employee-only runs $580-$780 PMPM, mid-market PPO $720-$980, and narrow network HMO/EPO $480-$680.
How do I avoid over-concentration on a few top brokers?
Cap any single broker near 8% of new annualized premium, require written succession plans for the top 25, and assign dedicated relationship managers to the top decile. If your top 25 brokers exceed 55% of NAP, build a formal retention program. Broker acquisitions by larger firms are common and can trigger rapid premium loss without a transition plan.
Sources
- https://www.cms.gov/medicare/health-drug-plans/medicare-advantage
- https://www.cms.gov/cciio/programs-and-initiatives/health-insurance-marketplaces
- https://www.healthcare.gov/quick-guide/dates-and-deadlines/
- https://www.kff.org/health-reform/
- https://www.ahip.org/
- https://www.naic.org/
- https://www.soa.org/
- https://www.milliman.com/en/insight
- https://www2.deloitte.com/us/en/insights/industry/health-care.html
Related on PULSE
This page will be disappearing soon. Save it to your device for $1 — or read it free while it is here.
@Kory-White- · if Venmo asks, the last 4 of my number are 2012
This page is gone.
This one is off the shelf now. $1 keeps it on your phone for good — the whole page, pictures and diagrams included.
 pulse-industry-kpisTop 10 KPIs for Roofing Contractors in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Online Travel Agency (OTA) in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Kitchen Hood & Exhaust Cleaning Services in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Insurance Brokerage in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Industrial Heat Treating & Metal Finishing Services in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Industrial Welding Equipment & Gas Distribution in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Carpet and Floor Care Services in 2027
 pulse-industry-kpisTop 10 KPIs for Barbershops in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Locksmith and Access Control in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Marketing Agency in 2027