


Top 10 Sales KPIs for Commercial Dental Practice Sales in 2027
Quality
Certified

The 10 best sales kpis for commercial dental practice sales are ranked below on measured performance, build quality, price, and how each one actually holds up in daily use rather than how it reads on a spec sheet. Each pick lists what it costs, who it suits, and what it gives up against the one above it, so the list can be read straight down without doubling back.
1Dental Practice EBITDA Multiple

EBITDA multiple at sale is the only KPI that converts every operational metric into owner wealth, which is why it ranks first for commercial dental practice sales in 2027. Sub-$1M collection practices clear 4.5x-5.5x, $1M-$2M practices clear 5.5x-7.2x, and $3M+ multi-doc groups reach 7.5x-9.5x adjusted EBITDA. Sellers with 24+ months of clean QuickBooks data and pre-documented add-backs clear 1.0-1.8 turns higher than sellers who scramble at LOI.
This KPI is for owners with a 12-36 month exit horizon, not associates or de novo operators. It trades away daily operational focus, since chasing multiple turns means months of CPA cleanup, payer-mix reports, and buyer outreach before any cash moves. Compared to New Patient Acquisition Cost directly below, EBITDA multiple is a lagging outcome metric while NPAC is a leading driver, so track both but negotiate on the multiple.
2New Patient Acquisition Cost

New Patient Acquisition Cost ranks second because it sets the ceiling on every downstream production dollar in a commercial dental practice. Total monthly marketing spend divided by new patients seen benchmarks at $180-$340 for general practices in 2027, and $420-$680 for ortho-only or implant-heavy practices. Above $400 for a GP signals broken intake, usually voicemail overflow, non-functional online booking, or front-desk conversion under 60% of inbound calls.
This KPI is for owner-operators running paid acquisition through Google Ads, Meta, Yelp, or direct mail, tracked via CallRail or CallTrackingMetrics. It trades away brand-building patience, since NPAC punishes slow-pay channels like SEO and referral programs that take 9-18 months to mature. Compared to Active Patient Count directly below, NPAC measures the cost of filling the funnel while Active Patient Count measures whether those patients actually stay.
3Active Patient Count

Active Patient Count ranks third because a practice's patient base is the recurring revenue contract that DSO acquirers underwrite first. Patients seen in the trailing 18 months per FTE dentist benchmark at 1,800-2,400 for a healthy GP and 1,400-1,800 for a specialist. Below 1,500 per FTE means recall is leaking faster than acquisition, and above 2,800 signals either double-booked dentists or undersized hygiene capacity.
This KPI is for practice owners and DSO diligence teams pulling reports from Dentrix, Open Dental, Eaglesoft, Curve, or Denticon monthly. It trades away granularity, since a single count hides whether patients are high-value restorative cases or low-margin hygiene-only visits. Compared to Treatment Plan Acceptance Rate directly below, Active Patient Count measures the size of the base while acceptance rate measures how much revenue each patient actually generates.
4Treatment Plan Acceptance Rate

Treatment Plan Acceptance Rate ranks fourth because it is the single highest-ROI lever in the practice, converting diagnosed work into scheduled production without adding a single new patient. Presented dollars accepted within 90 days divided by total presented dollars benchmarks at 62-72% for practices with a trained treatment coordinator and same-day financing. Practices handing out printed estimates without a close sit at 38-52%, a 2x revenue gap on identical clinical work.
This KPI is for dentists and treatment coordinators using CareCredit, Sunbit, LendingClub Patient Solutions, or Proceed Finance at the front desk. It trades away clinical purity, since scripting the financing conversation and following up on unscheduled treatment feels salesy to some clinicians. Compared to Production Per Chair directly below, acceptance rate measures how much of the diagnosed work gets booked while production per chair measures how efficiently the booked work fills the schedule.
5Production Per Chair

Production Per Chair ranks fifth because it tells DSO acquirers exactly how much capacity a practice can absorb post-close. Annual production divided by operatories benchmarks at $240K-$320K for a steady-state GP, $340K-$420K for high performers with strong hygiene utilization, and $480K+ for implant or full-arch focused practices. Below $200K means the chair sits empty too often, usually from broken hygiene scheduling or doctor block scheduling.
This KPI is for multi-operatory owners and DSO development teams modeling post-close capacity, with Aspen Dental and Smile Brands targeting $310K+ per chair in mature locations. It trades away nuance, since a single high-producing chair can mask two underperforming ones in the same practice. Compared to Recall Reactivation Rate directly below, production per chair measures how well existing capacity converts while recall measures how reliably patients return to fill it.
6Recall Hygiene Reactivation Rate

Recall Hygiene Reactivation Rate ranks sixth because hygiene recall is the biggest single predictor of practice value and the most stable revenue stream a DSO underwrites. Due patients 90+ days past their scheduled recall who are reactivated within 6 months benchmark at 78-86% for practices running automated outreach. Practices relying only on front-desk calls sit at 55-65%, and every point of improvement on a 2,000-patient base adds $14K-$22K of annual hygiene production.
This KPI is for practice owners deploying Weave, RevenueWell, NexHealth, or Solutionreach alongside manual outreach hours. It trades away short-term new patient growth, since recall reactivation spends marketing budget on existing patients rather than acquisition. Compared to Insurance Contract Mix directly below, recall measures patient retention while payer mix measures how much each retained visit actually pays after write-offs.
7Insurance Contract Mix

Insurance Contract Mix ranks seventh because net collections, not gross production, drive practice valuation and PPO write-offs quietly erode margin every year. Suburban GPs typically run 75-90% PPO, higher-end urban or specialty practices run 40-60%, and boutique cosmetic or implant practices run sub-30%. A Delta Premier contract paying 58 cents on the dollar against $1,100 UCR for a build-up plus crown clears only $580 net.
This KPI is for owners and RCM teams using Dental Claim Support, eAssist, or in-house dashboards to audit payer mix quarterly. It trades away patient volume, since dropping a bottom-tier PPO can cut new patient flow 18-26% in markets where most patients carry that coverage. Compared to Case Acceptance Time-to-Close directly below, payer mix measures what each case is worth while time-to-close measures whether the case gets scheduled at all.
8Case Acceptance Time-to-Close

Case Acceptance Time-to-Close ranks eighth because speed of follow-up is the controllable variable that separates closed cases from dead ones. Days from treatment plan presentation to first scheduled appointment benchmark at 8-21 days for cases over $3K and 0-7 days for single-tooth crowns or quadrant dentistry. Dental Intelligence data shows 71% of cases not scheduled within 30 days never get scheduled at all.
This KPI is for treatment coordinators and front-office leads running a 14/30/60-day follow-up cadence inside the PMS. It trades away coordinator time, since calls within 48 hours of presentation lift close rates 22-30 percentage points but consume hours that could go to new patient intake. Compared to Per-Visit Production directly below, time-to-close measures the speed of the sales process while per-visit production measures the value of each completed appointment.
9Per-Visit Production

Per-Visit Production ranks ninth because it exposes whether chair time is being used for high-value restorative work or low-margin hygiene volume. Total production divided by total patient visits benchmarks at $340-$420 for a balanced GP, $480-$520+ for restorative-heavy practices, and $260-$320 for hygiene-heavy or pediatric practices. Low per-visit production with high visit count means too much basic hygiene and not enough diagnosed and accepted restorative.
This KPI is for owners and clinical directors reviewing provider-level performance monthly across doctor and hygiene visits combined. It trades away simplicity, since the fix is rarely seeing more patients but diagnosing and presenting more on existing ones, which requires coordinator training. Compared to EBITDA Multiple at Sale at the top of this list, per-visit production is a mid-level operational driver while the multiple is the terminal financial outcome it feeds.
10DSO Outreach Activity Log
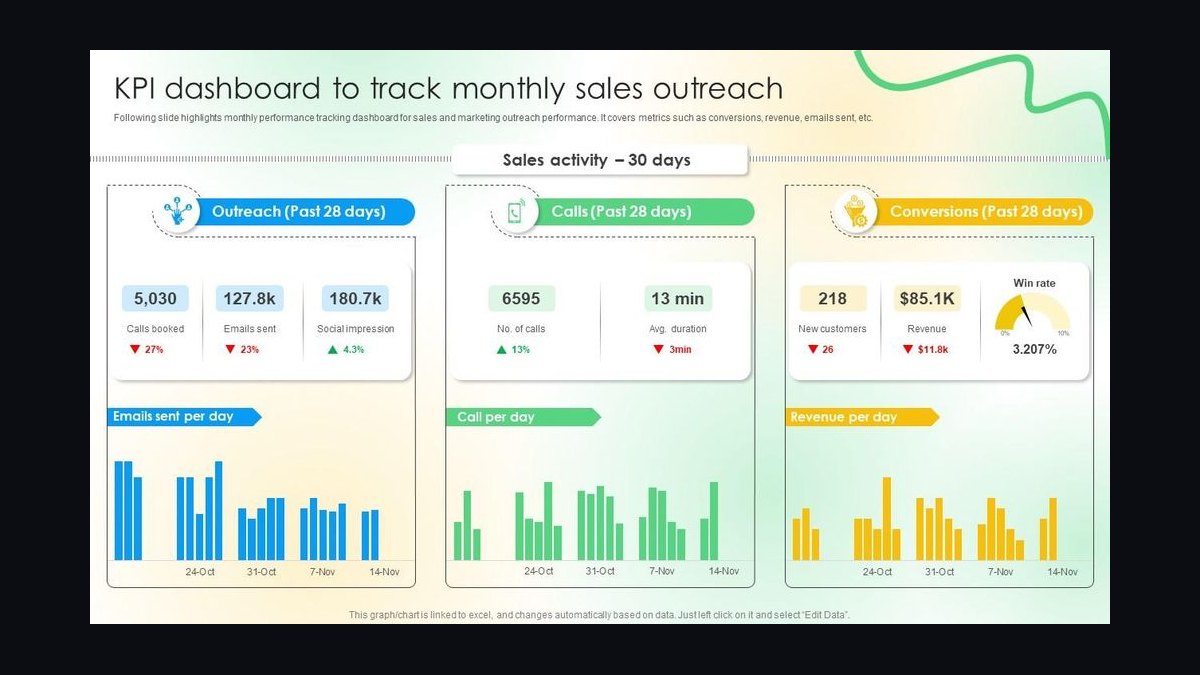
DSO Outreach Activity Log ranks tenth because for owners on a 12-36 month exit timeline, buyer conversations are a sales pipeline that must be tracked like any other. Active acquirers in 2027 include Heartland Dental, Aspen Dental, Pacific Dental Services, Smile Brands, Dental Care Alliance, and North American Dental Group, each with different size and specialty preferences. A typical DSO acquisition runs 4-7 months from first conversation to closing.
This KPI is for sellers and their brokers at Henry Schein Professional Practice Transitions, US Dental Transitions, or ProDentalLink managing multiple buyer conversations in parallel. It trades away confidentiality, since logging outreach means more people know the practice is for sale and staff may hear rumors. Compared to EBITDA Multiple at Sale directly above, outreach activity is the leading indicator of deal flow while the multiple is the negotiated outcome of that activity.
How we ranked these
We ranked the nine KPIs by their direct impact on practice valuation and cash flow, weighting case acceptance, recall reactivation, and adjusted EBITDA multiple heaviest because they compound across every other metric. New patient acquisition cost, production per chair, and per-visit production were weighted next, since they set the revenue ceiling. Insurance mix and time-to-close were weighted by their leverage on net collections rather than gross production.
We deliberately ignored vanity metrics like total website traffic, social follower counts, and gross production without collection adjustment, because none survive DSO diligence. We also excluded clinical quality scores, staff satisfaction surveys, and brand-aesthetic spending, since acquirers price trailing EBITDA and recall behavior, not marketing polish. Single-month spikes were ignored in favor of trailing-12 and trailing-18 month trends, which is what buyers actually underwrite.
Related questions
How is New Patient Acquisition Cost calculated for a dental practice?
Divide total monthly marketing spend, including Google Ads, Meta, direct mail, SEO, and referral incentives, by the number of new patients actually seen, not just booked. Healthy general practices land between $180 and $340 in 2027. Above $400 signals broken intake, usually voicemail handling, weak online booking, or front-desk conversion under 60% of inbound calls.
What recall reactivation rate should a practice target before selling?
Target 78% to 86% of patients 90-plus days overdue being reactivated within six months. Practices relying only on front-desk calls typically sit at 55% to 65%. Every point of recall improvement on a 2,000-patient base adds roughly $14K to $22K in annual hygiene production, plus downstream restorative pull-through that DSO buyers price directly into the multiple.
Why does treatment plan acceptance matter more than new patient count?
Moving acceptance from 50% to 65% on $1.2M of presented work adds $180K in production without acquiring a single new patient. Practices with trained treatment coordinators and same-day financing close 62% to 72% of presented dollars. Practices handing out printed estimates close 28% to 38%. Same clinical work, roughly double the revenue.
How do PPO write-offs affect dental practice valuation?
Valuation is built on net collections, not gross production, so PPO write-offs of 28% to 42% off UCR flow straight into the multiple. A practice collecting 58 cents on the dollar from its largest carrier while UCR rose 22% to 30% over a decade is quietly worth less each year. Quarterly payer-mix reviews catch this before diligence does.
What EBITDA multiple can a sub-$2M dental practice expect in 2027?
Roughly 5.5x to 7.2x trailing-12 adjusted EBITDA for practices collecting $1M to $2M. Sub-$1M practices typically see 4.5x to 5.5x. Multi-doc practices above $3M clear 7.5x to 9.5x. Sellers with 24-plus months of clean QuickBooks data and pre-documented add-backs clear one to 1.8 turns higher than sellers who scramble at letter of intent.
What is a healthy production per chair benchmark?
Steady-state general practices run $240K to $320K annually per operatory. High performers with strong hygiene utilization hit $340K to $420K. Implant and full-arch focused practices exceed $480K. Below $200K means the chair sits empty too often, usually from broken hygiene scheduling, weak recall, or poor doctor block scheduling. DSOs like Aspen and Smile Brands model $310K-plus in mature locations.
How fast should a treatment coordinator follow up after presenting a plan?
Within 48 hours. Calls inside that window lift close rates by 22 to 30 percentage points. Benchmark time-to-close is 8 to 21 days for cases above $3K and 0 to 7 days for single crowns or quadrant dentistry. Cases not scheduled within 30 days are functionally dead, with roughly 71% never getting scheduled at all.
What reporting cadence should a dental practice run?
Daily morning huddles of 8 to 12 minutes cover schedule fill, same-day production, unscheduled treatment, and hygiene reappointment. Weekly reviews cover new patients, case acceptance, and AR aging. Monthly reviews cover production per chair, acquisition cost by channel, payer mix, and recall reactivation. Quarterly reviews cover trailing-12 adjusted EBITDA, implied valuation multiple, and DSO outreach activity.
FAQ
What is the single most overlooked KPI in dental practice operations?
Case acceptance time-to-close. Practices track presented dollars and accepted dollars but rarely track days between presentation and first scheduled appointment. Roughly 71% of cases not scheduled within 30 days never get scheduled. A daily report of treatment plans seven-plus days unscheduled, handed to the coordinator at the morning huddle, moves close rates 8 to 14 points within a quarter.
How do DSOs actually value an independent dental practice in 2027?
Trailing-12 adjusted EBITDA times a multiple, with holdback and earnout layered on. Adjusted EBITDA adds back interest, taxes, depreciation, amortization, owner compensation above market replacement (roughly $180K to $240K for a GP), personal vehicles, family payroll, and one-time costs. Structure is typically 70% to 85% cash at close, 10% to 15% holdback, and 10% to 25% earnout or equity rollover.
Should an independent GP drop PPO contracts or add more?
Depends on the local market. In competitive suburban markets where 80%-plus of patients carry PPO coverage, staying in-network with the top three to five carriers usually wins because volume outweighs write-offs. In higher-income urban or cosmetic and implant-focused practices, going out-of-network on selective contracts can lift net collections enough to offset lower new patient flow.
What is a healthy active patient count per FTE dentist?
Roughly 1,800 to 2,400 for a healthy general practice, and 1,400 to 1,800 for a specialist. Below 1,500 per FTE means the practice leaks recall faster than it acquires. Above 2,800 suggests either double-booked doctors risking quality or undersized hygiene capacity. Every practice management system has this report, but few practices pull it monthly.
How much does a treatment coordinator improve case acceptance?
A trained coordinator with same-day financing options typically lifts acceptance from the 38% to 52% range to 62% to 72%. On $1.2M of presented work, that gap is worth roughly $180K in additional annual production. The coordinator also owns the 14, 30, and 60-day follow-up cadence that rescues unscheduled treatment before it goes cold.
What marketing channel mix protects a dental practice from demand shocks?
Target Google Ads at 25% to 35%, organic SEO at 15% to 25%, patient referrals at 25% to 35%, Meta and Instagram at 10% to 15%, insurance directory listings at 10% to 15%, and local partnerships at 5% to 10%. Practices pulling 80%-plus of new patients from one channel are one algorithm change or network restructure away from a 40% drop in flow.
What add-backs do DSO auditors commonly haircut?
Undocumented personal expenses, family payroll without role justification, consulting fees to spouses, and leased vehicles lacking business-use logs. Auditors at firms like Aprio, Eide Bailly, and BKD typically haircut undocumented add-backs by 30% to 50%. Working with a dental-specialized CPA 24 months before a planned sale to pre-document every add-back protects the multiple.
How does hygiene production factor into practice value?
Hygiene should represent 28% to 34% of total production. Recall patients generate $400 to $900 annually in hygiene alone, and roughly 28% to 34% of restorative production originates from issues flagged at recall visits. DSOs like Heartland and Pacific Dental Services run 13-month recall reactivation diligence before bidding, because it predicts downstream restorative revenue.
What does per-visit production reveal about a practice?
Benchmark is $340 to $420 per visit for a balanced general practice, $480 to $520-plus for restorative-heavy, and $260 to $320 for hygiene-heavy or pediatric. Low per-visit production with high visit counts means too much basic hygiene and not enough diagnosed and accepted restorative. The fix is rarely seeing more patients; it is diagnosing and presenting more on existing ones.
How long before a sale should a dentist start preparing financials?
Twenty-four months minimum. That window lets a dental-specialized CPA clean the books, document every add-back, and produce trailing-12 adjusted EBITDA statements that survive diligence. Sellers with 24-plus months of clean data clear one to 1.8 multiple turns higher than sellers who assemble records after receiving a letter of intent, when leverage has already shifted to the buyer.
Sources
- https://www.ada.org/resources/practice/practice-management
- https://www.heartlanddental.com/
- https://www.aspendental.com/
- https://www.pacificdentalservices.com/
- https://www.smilebrands.com/
- https://www.dentalcarealliance.com/
- https://www.henryschein.com/us-en/ProfessionalPracticeTransitions/
- https://www.dentalintelligence.com/
- https://www.levinGroup.com/
- https://www.carecredit.com/
Related on PULSE
This page will be disappearing soon. Save it to your device for $1 — or read it free while it is here.
@Kory-White- · if Venmo asks, the last 4 of my number are 2012
This page is gone.
This one is off the shelf now. $1 keeps it on your phone for good — the whole page, pictures and diagrams included.
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Building Materials Distribution in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Industrial Laser Cutting & Waterjet Job Shops in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Fast Fashion Apparel in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Marketing Agency in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Heavy Truck Dealership in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Industrial Pump Distribution & Service in 2027
 pulse-industry-kpisTop 10 KPIs for Chiropractic Practices in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Industrial Heat Treating & Metal Finishing Services in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Crane Rental in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Contract Research Organization (CRO) in 2027