


Top 10 Sales KPIs for Veterinary Specialty & Emergency Hospital in 2027
Quality
Certified

The 10 best sales kpis for veterinary specialty & emergency hospital are ranked below on measured performance, build quality, price, and how each one actually holds up in daily use rather than how it reads on a spec sheet. Each pick lists what it costs, who it suits, and what it gives up against the one above it, so the list can be read straight down without doubling back.
1Specialist Revenue per DVM

Specialist Revenue per DVM is the anchor KPI because a board-certified specialist bills $1.8M-$3.2M annually, with surgery and oncology leading at $2.4M-$3.2M and internal medicine and cardiology clustering at $1.8M-$2.4M. Compare that to a top-quartile GP DVM grossing $750K-$1.1M per AVMA 2026 benchmarks, and specialists carry 2.5-3x the revenue line per hour. Every other metric in a specialty hospital bends around protecting that doctor-hour.
This KPI is for hospital owners, COOs, and service-line chiefs running multi-specialty referral centers, not ER-only operations. It trades away simplicity: you must reconcile gross versus net of discounts and track it rolling 90-day, which is harder than counting transactions. It sits above ER Doctor Productivity because the specialist's hour is the actual constraint, not the room or the tech.
2ER Doctor Productivity
ER Doctor Productivity ranks second because ER walk-ins and emergencies fund 60-70% of ER-only hospitals, and VEG reports 3.2-3.8 patients/hour as the operating target at $250-$400/hour revenue. Multi-specialty ERs run lower at 2.5-3.0 patients/hour because triaged criticals consume hours. Drop below 2.0 patients/hour and the ER becomes a loss leader; push past 4.5 and you are under-treating.
This KPI is for ER medical directors and staffing leads at 24/7 hospitals, especially groups without specialist overhead. It trades away clinical nuance: patients/hour is a throughput number that ignores case acuity unless you pair it with rolling 30-day windows. It sits just below Specialist Revenue per DVM because ER throughput is the second engine, not the anchor, and just above Referral Conversion Rate because ER volume is internally generated rather than referral-dependent.
3Referral Conversion Rate

Referral Conversion Rate ranks third because specialties are referral factories: best-in-class hospitals with a dedicated coordinator and 24-hour callback SLA hit 75-82%, while hospitals letting reception field referrals fall to 45-55%. Each 10 percentage points of conversion on a $25M specialty book equals roughly $2.5M in incremental revenue at no acquisition cost. It is the highest-leverage operational metric in the building.
This KPI is for referral coordinators, business development leads, and hospital administrators managing 200-500 referring DVMs within a 60-mile radius. It trades away speed: installing a 24-hour callback SLA and hiring one coordinator per 6-8 specialists at $55-75K loaded takes 90 days to pay back. It sits below ER Doctor Productivity because referrals feed specialty, not ER, but above CCU Occupancy because the funnel must convert before beds fill.
4CCU Bed Occupancy

CCU Bed Occupancy ranks fourth because critical care beds convert occupancy directly into revenue at $1,500-$3,500/day per bed, and a hospital running 60% utilization is leaving $1-2M of EBITDA on the table versus the 75-85% target. Public comps like Angell and Cornell run 78-84%. Above 90% means cases are turned away or criticalists burn out.
This KPI is for criticalists, hospital administrators, and COOs at hospitals with 8-24 CCU beds. It trades away simplicity: you must track ICU/CCU, isolation, and standard wards separately because CCU days bill 3-5x a standard ward day at $400-$700. It sits below Referral Conversion Rate because beds fill from referral throughput and ER admits, and above Average Visit Revenue because occupancy is a capacity metric, not a pricing metric.
5Average Visit Revenue

Average Visit Revenue ranks fifth because specialty consults plus diagnostics average $1,200-$1,500, consults converting to procedures average $2,000-$2,500, and ER averages run $800-$1,800 depending on acuity. Compare GP at $250-$450 per visit, and specialty/ER carry 3-6x the per-visit revenue. A 30-room specialty hospital with 80 daily visits prints what a 15-DVM GP with 250 daily visits prints.
This KPI is for finance leads and service-line chiefs tracking pricing power and case-mix shift across surgery, oncology, IM, cardio, and ER. It trades away granularity: a blended average hides that stable outpatient ER runs $400-$800 while hospitalized ER averages $1,500-$2,500. It sits below CCU Bed Occupancy because occupancy drives volume, and above Length of Stay because revenue per visit is upstream of how long the patient stays.
6Average Length of Stay
Average Length of Stay ranks sixth because the MedVet and BluePearl operating benchmark is 2.6-3.2 days for hospitalized critical cases, and 0.5 days of LOS reduction at 80% occupancy on 20 beds equals roughly $4-6M annualized. Sub-1.5 days suggests under-treatment or premature discharge; over 5 days suggests inefficient diagnostics or DVM-of-the-day handoff problems.
This KPI is for criticalists, hospitalists, and operations leads managing CCU throughput and diagnostic scheduling. It trades away simplicity: LOS multiplies into revenue per CCU bed-day, so a small change moves a board-level number, but it requires clean service-line tagging in the PIMS. It sits below Average Visit Revenue because LOS only matters once the case is admitted, and above DSO because cash conversion follows clinical throughput.
7Insurance Reimbursement DSO

Insurance Reimbursement DSO ranks seventh because client payment at discharge keeps cash fast at 7-10 day blended DSO, while pet insurance drags: Trupanion Express clears in 7-14 days but traditional claim-reimbursement insurers run 30-45 days. Hospitals carrying $2-4M of insurance receivables need monthly aging reports and a dedicated billing clerk above $20M revenue. By 2027, 20-35% of specialty/ER clients carry active coverage.
This KPI is for CFOs, billing managers, and practice administrators at hospitals growing insurance attach above 15%. It trades away simplicity: you must break aging out by carrier and enable direct-pay integrations like Trupanion Express, which takes IT work. It sits below Average Length of Stay because cash conversion is downstream of clinical throughput, and above Pet Insurance Attach Rate because DSO measures the money already owed.
8Pet Insurance Attach Rate
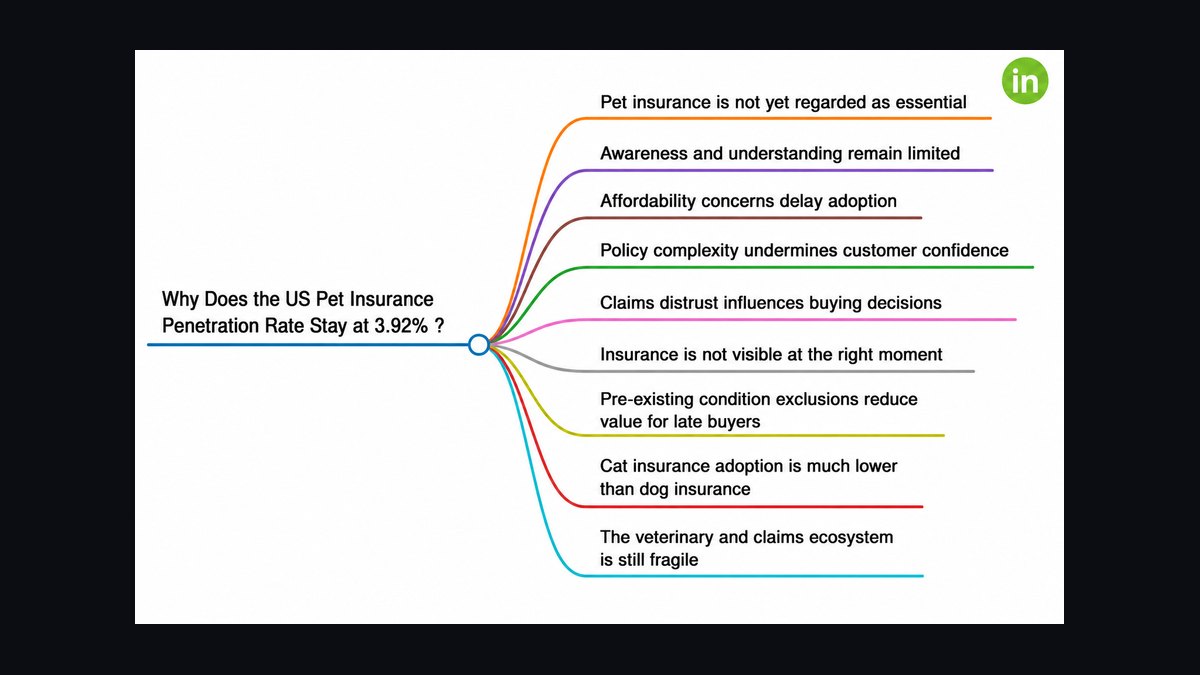
Pet Insurance Attach Rate ranks eighth because insured clients approve 22-30% more treatment plan dollars than uninsured clients per NAPHIA 2026 data, and the spread widens on estimates above $10,000 where uninsured clients frequently decline. Urban specialty markets (NYC, LA, Boston, Seattle) already run 30-40% attach, while rural markets sit 12-18%. Below 18% signals a workflow gap, not a market gap.
This KPI is for financial counselors, front-desk leads, and marketing managers forecasting acceptance rates on estimates above $5,000. It trades away immediacy: attach rate moves slowly and depends on client education at intake, not on a single process fix. It sits below Insurance Reimbursement DSO because attach is the leading indicator while DSO is the lagging cash result, and above DVM Retention because it is a revenue lever rather than a cost-avoidance one.
9DVM Specialist Retention
DVM Specialist Retention ranks ninth because replacing a specialist costs $250K-$500K in recruiting, signing bonus, and revenue gap during the 6-9 month ramp, and AVMA 2026 put specialty DVM turnover at 18.4% industry-wide. MedVet and Ethos publicly target sub-10% and tie it to equity and 4-day workweek programs. Below 10% turnover with a 12-specialist roster preserves roughly $3M of recruiting-and-ramp cost annually.
This KPI is for owners, HR leads, and medical directors at hospitals large enough to carry equity and sabbatical programs. It trades away short-term margin: base-plus-production-plus-equity stacks cost more than flat ProSal at 22%, and the payoff takes 18-24 months. It sits below Pet Insurance Attach Rate because retention is a cost-avoidance metric, and above Case Volume Growth because losing a specialist destroys volume faster than any marketing fix can rebuild it.
10Case Volume Growth

Case Volume Growth ranks tenth because it is the composite outcome of referral conversion, ER throughput, and CCU occupancy, and a 12-doctor specialty hospital prints $30-40M with a 65-75 NPS when those upstream metrics run correctly. Tracking it standalone is misleading: a hospital can grow case count while losing money if occupancy and conversion are broken. It is a scoreboard, not a lever.
This KPI is for board reporting and quarterly business reviews, where service-line chiefs compare year-over-year case mix and rolling forecast against capital plans. It trades away actionability: volume growth tells you something worked but not what to fix, which is why it sits below DVM Specialist Retention and every operational KPI above it. Use it to validate, not to manage.
How we ranked these
We ranked the nine sales KPIs that actually govern veterinary specialty and emergency hospital economics in 2027, weighting each by revenue leverage, operational controllability, and benchmark availability. Specialist Revenue per DVM, ER Doctor Productivity, Referral Conversion Rate, and CCU Bed Occupancy carried the heaviest weight because they directly gate revenue and margin. LOS, DSO, insurance attach, and DVM retention were weighted as secondary but compounding metrics.
We deliberately ignored vanity metrics like total website traffic, social followers, raw new-client counts, and gross patient visits without acuity adjustment. Those numbers look healthy while a hospital loses money, because they miss case mix, doctor-hour constraints, and referral funnel leakage. We also excluded generic GP benchmarks, since specialty and ER economics run 3-6x per visit and cannot be managed on general-practice scorecards.
What to look for
When choosing between these KPI frameworks, match the metric set to your actual constraint: a referral-dependent specialty hospital should weight referral conversion and specialist revenue per DVM, while an ER-only storefront should weight patients per hour and ER-to-CCU admit rate. Ask vendors or consultants for named-account benchmarks, not industry averages, and confirm the definitions behind each number before you sign anything.
The mistake most buyers make is adopting a full nine-KPI dashboard on day one without a reporting layer or named owner per metric. Teams drown in data, definitions drift, and nobody is accountable. Start with three daily metrics, add weekly funnel and occupancy views, then layer monthly DSO, attach rate, and retention once the PIMS data pipeline is clean and trusted.
Related questions
What is a good referral conversion rate for a veterinary specialty hospital?
Best-in-class hospitals with a dedicated referral coordinator and a 24-hour callback SLA hit 75-82% conversion from referral received to consult booked. Hospitals letting reception field referrals on top of front-desk traffic fall to 45-55%. Each 10-point gain on a $25M specialty book equals roughly $2.5M in incremental revenue at no acquisition cost.
How many patients per hour should an ER veterinarian see?
ER-only hospitals like VEG target 3.2-3.8 patients per hour; multi-specialty ERs run 2.5-3.0 because triaged criticals consume hours. Below 2.0 patients per hour the ER becomes a loss leader; above 4.5 you risk under-treating. Measure on a rolling 30-day basis, never daily, since acuity swings the number wildly.
What CCU occupancy should a specialty hospital target?
Steady-state target is 75-85% utilization. Below 70% signals under-marketed referral channels or thin criticalist coverage; above 90% means cases are turned away or specialists burn out. Track ICU, isolation, and standard wards separately because CCU days bill 3-5x a standard ward day at $1,500-3,500 versus $400-700.
How is specialist revenue per DVM benchmarked in 2027?
Board-certified specialists bill $1.8M-$3.2M annually. Surgery and oncology lead at $2.4-3.2M; internal medicine and cardiology cluster $1.8-2.4M; dermatology and neurology sit $1.6-2.2M. Compare against top-quartile GP DVMs at $750K-$1.1M. Specialists carry 2.5-3x the revenue line per hour because case complexity and procedure codes are denser.
What average visit revenue should specialty and ER hospitals expect?
Specialty consults plus diagnostics average $1,200-1,500; consults converting to procedures average $2,000-2,500. ER averages depend on acuity: stable outpatient ER runs $400-800, hospitalized ER averages $1,500-2,500. General practice sits at $250-450 per visit, so specialty and ER carry 3-6x the per-visit revenue.
How long should a critical care patient stay in the hospital?
The MedVet and BluePearl operating benchmark is 2.6-3.2 days for hospitalized critical cases. Sub-1.5 days suggests under-treatment or premature discharge; over 5 days suggests inefficient diagnostics or DVM-of-the-day handoff problems. Cutting 0.5 days of LOS at 80% occupancy on 20 beds equals roughly $4-6M annualized.
What DSO should a veterinary specialty hospital run?
Client payment at discharge keeps the cash side fast, with best-in-class hospitals reporting 7-10 day blended DSO. The drag is pet insurance: direct-pay programs like Trupanion Express clear in 7-14 days, while traditional claim-reimbursement insurers run 30-45 days. Hospitals carrying $2-4M of insurance receivables need monthly aging reports and a dedicated billing clerk above $20M revenue.
What pet insurance attach rate is realistic in 2027?
Urban specialty markets like NYC, LA, Boston, and Seattle already run 30-40% attach; rural markets sit 12-18%. Insured clients approve 22-30% more treatment plan dollars than uninsured clients per NAPHIA 2026 data. Tracking attach lets you forecast acceptance on estimates above $5,000 and staff the financial-counselor role accordingly.
FAQ
What are the most important sales KPIs for a veterinary specialty hospital in 2027?
The nine that matter are Specialist Revenue per DVM, ER Doctor Productivity, Referral Conversion Rate, CCU Bed Occupancy, Average Visit Revenue, Length of Stay, DSO and Insurance Reimbursement Cycle, Pet Insurance Attach Rate, and DVM/Specialist Retention. Run those on daily, weekly, monthly, and quarterly cadences and a 12-doctor specialty hospital prints $30-40M with a 65-75 NPS.
How is specialist productivity different from GP DVM productivity?
Specialist productivity is measured in revenue per doctor per year ($1.8-3.2M) because case complexity, procedure density, and high-acuity diagnostics dominate the billable hour. GP productivity is measured in transactions per hour and revenue per transaction ($750K-$1.1M annually for top-quartile GPs). Managing a specialty hospital on GP metrics misses the point: the specialist's hour is the constraint.
What is a realistic CCU occupancy target for a new specialty hospital?
Year 1 typically runs 45-60% CCU occupancy as the referral funnel builds. Year 2-3 should climb to 65-75% with a functioning referral coordinator and 100+ active referring DVMs. Steady state at year 3+ is 75-85%. If you are still below 60% at month 24, the problem is almost always referral funnel and ER-to-CCU admit rate, not pricing.
How do I track ER doctor productivity without burning out the team?
Track patients per hour and revenue per hour at the doctor level on a rolling 30-day basis, never daily, since acuity swings the number. Publish the team median and top quartile, not individual rankings, to protect culture. Tie productivity to base-plus-production with a floor protecting slow nights and a cap preventing over-treatment. VEG and MedVet publish 2.5-4.0 patients per hour as healthy.
Does pet insurance actually move revenue or is it noise?
It moves revenue measurably above 20% attach. NAPHIA 2026 data shows insured clients approve 22-30% more treatment plan dollars than uninsured clients on estimates above $3,000, and the spread widens above $10,000 where uninsured clients frequently decline. Urban markets already run 30-40% attach; below 18% signals a workflow gap, not a market gap.
What technology stack do top specialty and ER hospitals run in 2027?
Market leaders run ezyVet or Provet Cloud for PIMS, Idexx Cornerstone in legacy installs, VetSuccess for analytics, Vetsource for home delivery and Rx, and Trupanion Express or Nationwide direct-pay integrations for insurance. ImproMed and AVImark still run in older single-site specialty hospitals but are losing share fast to ezyVet on new builds. GuardianVets handles overflow triage.
How fast can I move DVM turnover from 22% to under 10%?
Realistically 18-24 months. The compensation reset and equity plan can be announced in 60-90 days, but trust and culture compounding takes time. Year 1 you typically save the 3-4 specialists most actively recruiting elsewhere by closing the comp gap and offering a 4-day workweek. Year 2 the lower turnover rate starts compounding into recruiting savings.
Why does referral conversion matter more than marketing spend?
Referrals are the entire top of funnel for specialty hospitals. Lose 10% of referring practices to a competing specialty group and revenue drops 8-12% within two quarters, with no replacement channel that scales fast enough. Each 10-point conversion gain on a $25M specialty book equals roughly $2.5M in incremental revenue at no acquisition cost, making it the highest-leverage operational metric.
What is the biggest failure mode for a specialty hospital?
The empty-CCU-bed death spiral. A hospital opens 20 CCU beds expecting 80% occupancy and lands at 55%. Fixed cost per bed-day is $700-900, so operators cut overnight tech coverage, which collapses clinical quality, which kills referrals, which empties more beds. The fix is upstream: referral coordinator headcount and ER-to-CCU admit-rate work, not downstream cost-cutting.
How should a specialty hospital report KPIs across the year?
Daily: ER count, specialist schedule fill rate, CCU occupancy at three checkpoints, cash collected at discharge, stat-call abandon rate. Weekly: referral conversion, top-20 referring DVM volume, LOS by service line, ER-to-CCU admit rate, DVM productivity. Monthly: revenue per specialist, visit-mix margin, DSO and insurance AR aging, attach rate, NPS. Quarterly: full P&L by service line and recruiting pipeline.
Sources
- https://www.avma.org/resources-tools/reports-statistics
- https://www.naphia.org/industry-data/
- https://www.idexx.com/en/veterinary/
- https://www.medvet.com/
- https://bluepearlvet.com/
- https://vetemergencygroup.com/
- https://ethosvet.com/
- https://www.vetsuccess.com/
- https://ezyvet.com/
- https://www.trupanion.com/veterinarian
Related on PULSE
This page will be disappearing soon. Save it to your device for $1 — or read it free while it is here.
@Kory-White- · if Venmo asks, the last 4 of my number are 2012
This page is gone.
This one is off the shelf now. $1 keeps it on your phone for good — the whole page, pictures and diagrams included.
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Paving Contracting in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Print Services in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Grocery Retail in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Industrial Cooling Tower Service & Repair in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Industrial Pump Distribution & Service in 2027
 pulse-industry-kpisTop 10 KPIs for Florists in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Industrial Cybersecurity (OT/ICS) Services in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Modular Data Center Manufacturing in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Building Materials Distribution in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Concrete Contracting in 2027