


Top 10 Best Tech Stack Tools for Virtual Healthcare and Telemedicine Startups in 2027
Quality
Certified
The 10 best tech stack tools for virtual healthcare and telemedicine startups are ranked below on measured performance, build quality, price, and how each one actually holds up in daily use rather than how it reads on a spec sheet. Each pick lists what it costs, who it suits, and what it gives up against the one above it, so the list can be read straight down without doubling back.
1Epic EHR

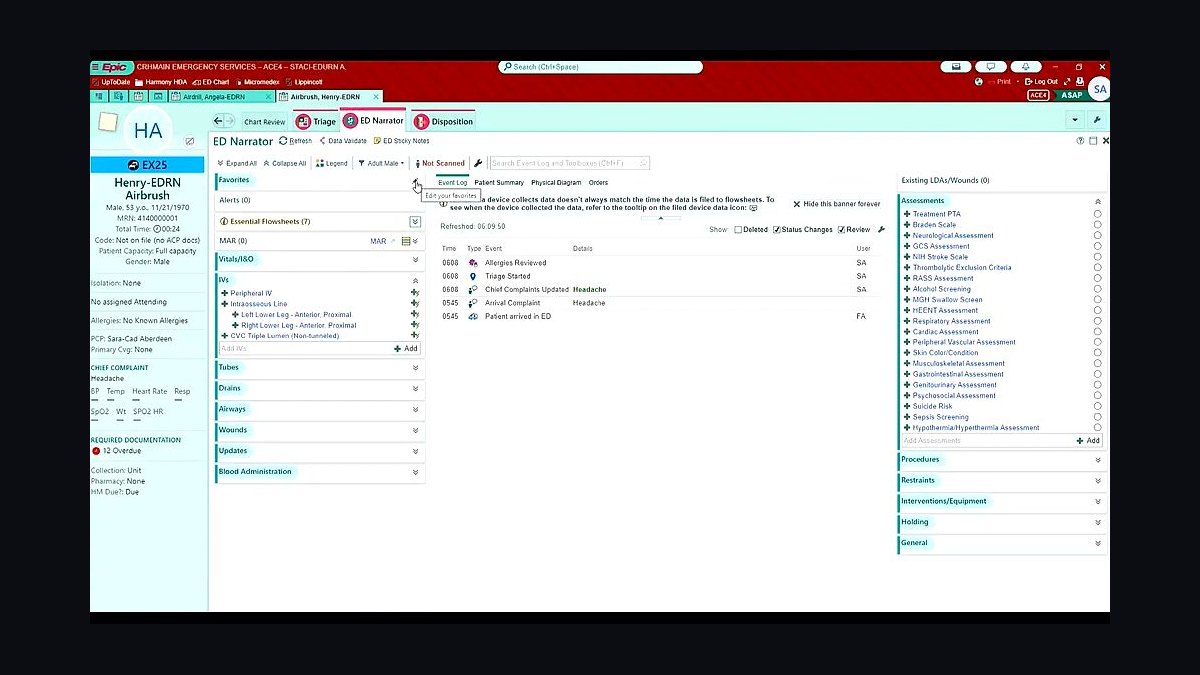
Epic ranks first because it is the only EHR in this stack with the interoperability depth that 50-plus-provider virtual-first clinics need across multiple states. Its FHIR APIs, Care Everywhere exchange, and mature telehealth module let encounter records write back the moment a video visit ends, with modifier 95 coding built into the billing workflow.
Epic is built for enterprise-scale virtual-first clinics, not solo or two-provider practices, where its implementation cost and complexity are hard to justify. It trades away simplicity and speed of deployment for interoperability and clinical depth. Compared with Athenahealth directly below it, Epic wins on multi-state, multi-specialty scale but loses badly on time-to-first-visit for a startup under 50 providers.
2Athenahealth EHR

Athenahealth ranks second because it is the cloud-native EHR that best fits the 10-to-50-provider tier, where multi-specialty billing and FHIR-based interoperability start to matter more than raw simplicity. Its built-in revenue cycle management handles telehealth modifiers and payer-specific parity rules without a separate billing vendor, and its cloud architecture means no on-premise infrastructure. For a growing virtual practice, that combination removes an entire integration project from the roadmap.
Athenahealth is aimed at growing multi-provider virtual practices, not solo therapists or 100-plus-provider enterprises. It trades away some of Epic's deep inpatient and multi-state exchange capability, and its per-provider pricing scales with headcount. Against Epic above it, Athenahealth is faster to deploy and cheaper at mid-scale; against Practice Fusion below it, it costs more but carries billing and interoperability the lighter tool cannot.
3Amwell Telehealth Platform

Amwell ranks third because it is the full-featured telehealth platform that bundles scheduling, billing, device integration, and multi-state provider network support into one enterprise-grade product. For a 50-plus-provider virtual-first clinic, that bundling removes several point-to-point integrations that would otherwise need FHIR middleware. Amwell signs a BAA, encrypts data in transit and at rest, and supports the asynchronous store-and-forward visits common in teledermatology and telepsychiatry.
Amwell is built for enterprise-scale virtual clinics, not two-provider practices, where its feature set and contract minimums are runway spent on unused capability. It trades away the light-touch simplicity of Doxy.me below it and the modularity of a best-in-class-per-layer stack. Compared with Doxy.me, Amwell wins on scale and bundled billing but loses on price and time-to-first-visit for a solo provider.
4Doxy.me Telehealth

Doxy.me ranks fourth because it is the browser-based telehealth tool that requires no patient download and no app install, which is the single biggest friction reducer for a solo or two-provider virtual practice. It signs a BAA, is HIPAA-compliant by default, and its free and low-cost tiers make it the lightest viable compliant video layer for a telepsychiatry or direct-to-consumer practice. A patient clicks a link and is in the visit.
Doxy.me is aimed at solo and small practices, not multi-provider clinics that need bundled scheduling, billing, and device integration. It trades away the enterprise feature set of Amwell above it and the deep EHR write-back that larger stacks require. Against Amwell, Doxy.me wins on price and simplicity but loses on scale, billing, and multi-state provider network support.
5Practice Fusion EHR

Practice Fusion ranks fifth because it is the lightweight cloud EHR that fits a solo or two-provider virtual practice that does not yet need Athenahealth's billing depth or Epic's interoperability. It is browser-based, signs a BAA, and covers the chart, medication history, lab results, and clinical notes that make a small virtual practice defensible in a malpractice review and billable to a payer. For a startup validating its clinical model, that is the minimum compliant spine.
Practice Fusion is for solo and small virtual practices, not growing multi-provider clinics where multi-specialty billing and FHIR interoperability start to matter. It trades away the revenue cycle management and interoperability of Athenahealth above it. Against Athenahealth, Practice Fusion wins on cost and deployment speed but loses on billing automation, multi-state support, and integration depth.
6Luma Health

Luma Health ranks sixth because it is the patient engagement layer that consolidates booking, secure messaging, and results delivery into one patient-facing surface, which is the highest-leverage fix for the fragmented-experience failure mode. When a patient needs a separate link for video, a different portal for scheduling, and a third channel for messaging, no-shows rise and satisfaction falls. Luma Health closes those seams without replacing the EHR or the video tool.
Luma Health is for growing virtual practices that already have a stable EHR and telehealth layer and are losing retention to integration seams. It trades away being a system of record, so it must integrate with whatever EHR sits above it. Against Phreesia below it, Luma Health leans more toward messaging and scheduling automation; Phreesia leans more toward intake and payments at the front desk.
7Phreesia Patient Intake

Phreesia ranks seventh because it handles the patient intake and payment layer that most virtual stacks leave to a generic form and a bolted-on processor. It captures demographics, insurance, consent, and copay before the visit, which reduces front-desk rework and no-shows for a multi-provider virtual practice. It integrates with major EHRs and signs a BAA, so it stays inside the compliance perimeter.
Phreesia is for multi-provider virtual practices with enough visit volume to justify a dedicated intake and payments layer, not solo practices where the EHR's built-in forms suffice. It trades away clinical charting, so it must sit alongside an EHR. Against Luma Health above it, Phreesia is stronger on intake and payments but weaker on post-visit messaging and scheduling automation.
8Redox FHIR Middleware

Redox ranks eighth because it is the FHIR-based integration engine that becomes its own budget line item once a virtual clinic runs 50-plus providers and multiple point-to-point vendor connections. The number of integrations grows faster than provider headcount, and a startup that has not budgeted for middleware discovers the gap during its third or fourth EHR integration project. Redox abstracts those connections behind one API.
Redox is for enterprise-scale virtual clinics with many vendor integrations, not small practices where direct EHR APIs are enough. It trades away being a clinical or patient-facing product, so it only pays off when integration count is high. Against Mirth Connect below it, Redox is more managed and cloud-native; Mirth Connect is more self-hosted and configurable for teams with integration engineers.
9Mirth Connect

Mirth Connect ranks ninth because it is the self-hosted integration engine that gives a virtual clinic's engineering team full control over HL7 and FHIR message routing without a per-connection vendor fee. For a startup with integration engineers on staff, that control can be cheaper at high message volume than a managed middleware product. It handles the device-to-EHR bridge that RPM and lab feeds require.
Mirth Connect is for virtual clinics with in-house integration engineering, not small practices without that capacity. It trades away the managed support and cloud-native operations of Redox above it, so it demands more operational ownership. Against Redox, Mirth Connect wins on cost control and configurability but loses on time-to-integration and vendor-managed reliability.
10Tableau Healthcare Analytics

Tableau ranks tenth because it is the BI layer that turns visit, billing, and no-show data into operational tuning once a virtual clinic has enough volume to make analysis meaningful. It connects to EHR and practice management data sources, and healthcare-specific dashboards track provider utilization, payer mix, and telehealth parity revenue. For a 50-plus-provider virtual-first clinic, that visibility is what separates a scaled operation from a guessing one.
Tableau is for enterprise-scale virtual clinics with enough visit and billing volume to justify dedicated BI, not small practices where the EHR's built-in reporting covers the need. It trades away being a clinical or operational system, so it depends entirely on the data quality of the stack beneath it. Against Luma Health and Phreesia above it, Tableau is analytical rather than patient-facing, and it should come last in the rollout sequence.
How we ranked these
We ranked tools by weighting HIPAA/BAA readiness and EHR interoperability first, since those determine whether a stack is legally usable at all. Next came telehealth-specific billing support (modifier 95, payer parity, asynchronous visits), then remote patient monitoring device integration, patient-facing consolidation, total cost at 10-50 provider scale, and vendor lock-in risk. Scores were assigned per layer rather than per brand, because the strongest 2027 stacks are modular.
We deliberately ignored headline pricing, marketing feature lists, and demo polish. Sticker price says little when BAA scope, integration middleware, and compliance staffing dominate real cost. We also excluded AI triage hype, app-store ratings, and any vendor's claimed "all-in-one" positioning, since bundled platforms most often fail exactly when a startup adds chronic care or a new payer relationship. Clinical outcomes claims were left out entirely — they reflect care model, not software.
What to look for
What actually matters is whether each vendor signs a BAA covering its own subcontractors and hosting, whether it exposes FHIR APIs for two-way chart writes, and whether it understands telehealth coding rather than generic appointment billing. Match tier to stage: a two-provider practice needs Doxy.me plus a lightweight EHR, while a 20-provider multi-specialty group needs Athenahealth-grade billing and real interoperability. Buy for the next twelve months, not the hoped-for enterprise future.
The mistake most buyers make is choosing the video platform first because it is visible and demo-friendly, then retrofitting an EHR around it. That inverts the hierarchy: the EHR is the spine, and every other tool must prove it can write into that record. The second common error is skipping compliance infrastructure early to ship faster, which converts a manageable HIPAA event into an existential one during diligence or breach response.
Related questions
Why should the EHR be chosen before the telehealth video platform?
The EHR holds the chart, medications, labs, and notes that make a virtual practice billable and defensible in a malpractice review. Choosing it first forces every later vendor to prove FHIR or API integration into the clinical record. Pick video first and you retrofit a chart around whatever tools you happened to buy.
What exactly must a Business Associate Agreement cover?
A BAA must extend to the vendor's own subcontractors and hosting infrastructure, not just the vendor itself. That gap is common with smaller point-solution vendors that outsource infrastructure. Verify encryption at rest and in transit, audit logging, and breach notification timelines are specified, and re-verify whenever a vendor changes its underlying cloud provider.
When does remote patient monitoring justify its own layer?
RPM earns its place once a startup manages ongoing chronic conditions such as hypertension, diabetes, or heart failure, where continuous device data changes care decisions. Acute-care-only startups can defer it. If added, integrate through FHIR into the EHR from day one rather than running a disconnected dashboard that fuels alert fatigue.
How does telehealth billing differ from standard medical billing?
Telehealth encounters require modifier 95, payer-specific parity rules that vary by state and plan, and support for asynchronous store-and-forward visits common in teledermatology and telepsychiatry. Generic scheduling tools with a payment processor bolted on typically cannot handle these, which pushes manual work onto billing staff and slows month-end close.
Is a single all-in-one platform safer than a modular stack?
All-in-one platforms reduce early integration work but often lack deep EHR interoperability or RPM device support. The gap surfaces exactly when a chronic-care contract or new payer demands capability quickly. A modular stack connected through standardized FHIR APIs lets you swap one layer without rebuilding the rest, which is usually the cheaper long-run choice.
What causes fragmented patient experience in virtual care?
Separate links for video, a different portal for scheduling, and a third channel for secure messaging turn the seams between tools into the patient's lived experience. Retention and no-show metrics degrade before anyone labels it an integration problem. Consolidating touchpoints through one engagement layer such as Luma Health or Phreesia is the highest-leverage fix.
How should multi-state licensure be handled technically?
Use a platform supporting multi-state provider networks, paired with a credentialing service or clinician network that manages licensure at scale. Interstate compacts help but do not cover every state or profession. Startups expanding faster than credentialing capacity hit a growth-stage bottleneck that is entirely avoidable with the right vendor partnership.
Should AI triage be built before rule-based automation?
No. Start with rule-based symptom-and-timing logic that triggers defined messages or routing actions, prove the workflow with real patients, then add API-based AI such as clinical NLP or conversational scheduling. Over-investing in custom AI infrastructure before the underlying clinical workflow is validated is a recognizable pattern behind avoidable digital health failures.
FAQ
Do I need a full EHR from day one as a solo provider?
Not always. A solo therapist can start with a lightweight telehealth tool plus basic practice management, adding a full EHR once volume or prescribing needs justify it. Any startup prescribing medication or managing chronic conditions needs an EHR immediately, regardless of provider count, because the clinical record is the billing and liability backbone.
Can Zoom Free or Google Meet work for telemedicine visits?
No. Neither signs a Business Associate Agreement, which makes them non-compliant for clinical use no matter how much they save. Use a platform built for healthcare that offers a signed BAA by default, or a general video API where a BAA is explicitly in place before any patient data touches the session.
How is virtual care billing different from in-person billing?
Telehealth visits require modifiers such as 95, payer-specific parity rules, and support for asynchronous store-and-forward encounters. Generic scheduling and billing tools typically lack these, forcing staff to flag every virtual visit manually. Practice management software purpose-built for telehealth prevents that manual overhead and reduces claim denials.
When does remote patient monitoring become necessary?
RPM becomes necessary once a startup manages ongoing chronic conditions like hypertension, diabetes, or heart failure, where continuous device data materially changes care decisions. Acute-care-only startups can usually defer it. When added, bridge devices to the EHR through FHIR and surface only clinically actionable alerts to avoid alert fatigue.
What is the biggest structural mistake in building this stack?
Centering the architecture on the telehealth video platform instead of the EHR. Video is a transport layer; the EHR is the spine. Treating video as primary leaves the startup without a trustworthy, billable chart, and providers end up re-keying the same information across disconnected systems.
How much does compliance overhead shrink for a small practice?
It does not shrink at all. A two-provider virtual practice needs the same BAA coverage, AES-256 encryption at rest, TLS 1.2-or-higher in transit, and audit logging as a fifty-provider group. What scales is dedicated staff time, so small teams should favor vendors that handle compliance configuration by default.
What is the risk of buying an enterprise stack too early?
Overbuilding before validating the clinical model burns runway on infrastructure that may not match your eventual specialty mix. Startups provisioning RPM, AI triage, and enterprise BI before proving the core visit workflow often discover the tools fit a patient population they never actually acquired. Start minimal, validate, then layer.
How do I avoid vendor lock-in in a telemedicine stack?
Favor modular, best-in-class tools per layer connected through standardized FHIR APIs rather than one proprietary ecosystem. Lock-in becomes visible only at scaling, when a bundled platform lacks the RPM device support or EHR interoperability a new contract demands. Modularity lets you replace a single layer without rebuilding everything.
What should be documented before signing any vendor contract?
Write a compliance baseline first: which data categories you collect, which vendors touch them, and the BAA and encryption requirements for each. This becomes the checklist every vendor decision is measured against, and it is the artifact investors and acquirers request first during due diligence.
Does a patient portal really need to be separate from the EHR?
Often yes, because EHR-native portals vary widely in usability and engagement features. A dedicated engagement layer such as Luma Health or Phreesia can unify booking, messaging, and results delivery across systems. The key requirement is bidirectional sync so portal activity writes back into the clinical record rather than living apart.
Sources
- https://www.hhs.gov/hipaa/for-professionals/covered-entities/index.html
- https://www.cms.gov/medicare/telehealth
- https://www.hl7.org/fhir/
- https://www.healthit.gov/topic/interoperability
- https://www.cdc.gov/telehealth/index.html
- https://www.fda.gov/medical-devices/digital-health-center-excellence
- https://www.himss.org/resources-telehealth
- https://www.ama-assn.org/practice-management/digital/telehealth
Related on PULSE
This page will be disappearing soon. Save it to your device for $1 — or read it free while it is here.
@Kory-White- · if Venmo asks, the last 4 of my number are 2012
This page is gone.
This one is off the shelf now. $1 keeps it on your phone for good — the whole page, pictures and diagrams included.
 tkTop 10 Best Tech Stack Tools for Cannabis Dispensary Chains in 2027
 tkTop 10 Best Tech Stack Tools for Lawn Care and Landscaping Companies in 2027
 tkTop 10 Best Tech Stack Tools for Direct-to-Consumer (DTC) Apparel Brands in 2027
 tkTop 10 Best Tech Stack Tools for Managed IT Services Providers (MSPs) in 2027
 tkTop 10 Best Tech Stack Tools for Property and Casualty Insurance Brokers in 2027
 tkTop 10 Best Tech Stack Tools for First-Time Business Owners in 2027
 tkTop 10 Best Tech Stack Tools for Third-Party Logistics (3PL) Warehouse Operators in 2027
 tkTop 10 Best Tech Stack Tools for Concrete and Paving Contractors in 2027
 tkTop 10 Best Tech Stack Tools for Fencing and Deck Contractors in 2027
 tkTop 10 Best Tech Stack Tools for Private Equity Portfolio Companies in 2027