
Top 10 Sales KPIs for Retail Pharmacy Chain in 2027
 Curated byKory White · Fractional CRO · Maryland
 PULSEKNOWLEDGE LIBRARY
Quality
Certified

The 10 best sales kpis for retail pharmacy chain are ranked below on measured performance, build quality, price, and how each one actually holds up in daily use rather than how it reads on a spec sheet. Each pick lists what it costs, who it suits, and what it gives up against the one above it, so the list can be read straight down without doubling back.
1. Retail Pharmacy Scripts Per Store Per Day

Scripts dispensed per store per day ranks first because every downstream margin number multiplies against it, making it the volume engine a district manager checks before anything else. CVS-scale stores average 200–350 scripts daily, the busiest urban locations exceed 600, and Walgreens' roughly 8,200 U.S. stores filling about 820M scripts annually implies roughly 275 per store per day. Below 150 scripts per day, dispensing margin cannot cover the pharmacist, and the location becomes a rightsizing candidate.
This KPI is built for integrated-margin operators like CVS and Walgreens where the pharmacy itself is the profit center. It trades away nothing directly, but it is a poor headline number for traffic-driver chains such as Walmart, Costco, and Kroger, where pharmacy is single-digit percent of store revenue and basket lift matters more than fill count.
2. Retail Pharmacy Gross Margin Per Script

Gross margin per script ranks second because volume alone cannot rescue a store whose dispensing economics are underwater. The metric has compressed from roughly $12 in 2018 to $8–$10 by 2026 per Drug Channels Institute estimates, and independents fall below $6 on many generic claims. At an integrated-margin store filling 275 scripts a day at $9 margin, dispensing throws off about $2,475 daily, enough to cover the pharmacist but little else.
This KPI is for CFOs and PBM-contract owners at chains that live or die on the MAC-plus-dispensing-fee spread. It trades away simplicity, since the number moves with mix, 90-day fills, specialty add-ons, and DIR fee clawbacks that land weeks after the fill.
3. Retail Pharmacy Generic Dispensing Rate

Generic dispensing rate ranks third because it is the cleanest direct margin lever a pharmacy chain controls without renegotiating contracts. Industry-wide GDR sits near 90% per IQVIA, with best-in-class chains at 91–93%, and at CVS's roughly 1.6B annual scripts a single point of improvement can be worth $50–$100M in gross profit. Generics carry a higher percentage spread even though absolute revenue per script is lower than brands.
This KPI suits chains with the formulary-adherence infrastructure to move prescribers and patients toward generic alternatives. It trades away revenue per script, since brand conversions lower top-line dollars even as they lift percentage margin. Compared with gross margin per script above it, GDR is a leading indicator: a low-GDR outlier store usually signals a prescriber-mix or formulary problem, while margin per script shows the financial damage after the fact.
4. Retail Pharmacy Clinical Services Revenue Per Store

Clinical-services revenue per store ranks fourth because it is the highest-margin growth line available to a chain with an existing pharmacist workforce. Immunizations, point-of-care testing, MTM, and Test-and-Treat carry 50–70% gross margins with no inventory to carry; top-decile stores cleared $400K+ in peak COVID years, and the steady state is $150K–$300K and growing. MinuteClinic and VillageMD-type partnerships push the structural ceiling toward $500K+.
This KPI is for integrated-margin chains willing to staff and bill for clinical work rather than pilot it and abandon it. It trades away pharmacist dispensing time, since every immunization or POCT visit consumes productive hours that could fill scripts. Compared with generic dispensing rate above it, clinical revenue improves both the margin line and the Medicare Star Rating, making it one of the few metrics that lifts two others simultaneously.
5. Retail Pharmacy Front-End Sales Share

Front-end retail sales as a share of revenue ranks fifth because it is the operating-leverage swing that determines whether a store survives a dispensing shortfall. Front-end runs about 22–25% of revenue at CVS and 28–32% at Walgreens versus single digits at grocery-based chains, and it carries 30–40% gross margin against 20–24% on pharmacy. That spread is why front-end attach matters even when script volume is flat.
This KPI is for integrated-margin chains with meaningful general-merchandise square footage, not for Costco or Walmart where pharmacy exists to pull the grocery basket. It trades away focus, because the trap is coupling: when pharmacy foot traffic falls, front-end basket attach craters in parallel, so a struggling store cannot simply grow the front end out of a dispensing shortfall. Compared with clinical-services revenue above it, front-end is lower-margin and more inventory-intensive.
6. Retail Pharmacy Medicare Part D Star Rating

Medicare Part D Star Rating ranks sixth because it governs network inclusion and bonus payments rather than store-level economics. The 1–5 score measures proportion of days covered for diabetes, hypertension, and statins plus MTM completion and patient experience. A 4.0+ rating drives bonus payments and preferred-network inclusion, while a drop from 4.5 to 3.5 can move tens of millions at chain scale as plans steer beneficiaries elsewhere.
This KPI is for chains with heavy Medicare Part D exposure and PBM contracts that reward adherence performance. It trades away short-term dispensing flexibility, since adherence interventions consume pharmacist and technician time before they pay off in ratings. Compared with front-end sales share above it, Star Rating is slower-moving and chain-wide rather than store-specific, but falling below 4.0 can vaporize 10–20% of script volume in a single PBM contract cycle.
7. Retail Pharmacy Digital Fulfillment Share

Digital-script fulfillment share ranks seventh because it is one of the few metrics that improves two others simultaneously. Both CVS and Walgreens report 20%+ digital script initiation, while Amazon Pharmacy is essentially 100% digital and competes on RxPass subscription pricing and same-day delivery in 50+ metros. Mature digital fulfillment lifts adherence, which lifts the Star Rating, and lowers per-script labor cost.
This KPI is for chains with the app, web, and delivery infrastructure to move fills out of the counter line. It trades away physical-footprint justification, since fills moving to mail and same-day delivery no longer need as many counters, which pushes integrated-margin chains toward rightsizing faster than reimbursement pressure alone would. Compared with Medicare Part D Star Rating above it, digital share is a leading signal rather than a scored outcome.
8. Retail Pharmacy Specialty Mix
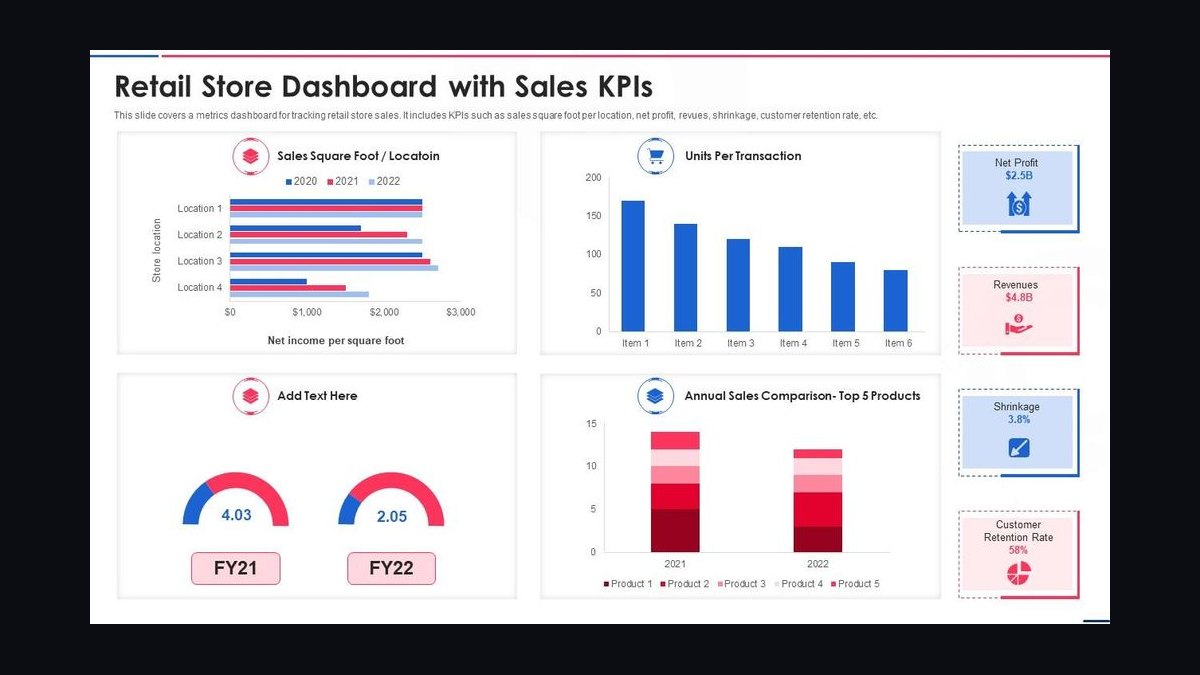
Specialty-pharmacy mix ranks eighth because it is small in script count but disproportionately important to revenue per fill. Specialty drugs are 2–3% of national volume and over 50% of drug spend, while retail-store specialty is 1–4% of scripts at most chains. Retail-store specialty is a smaller line than the big specialty pharmacies, since CVS Specialty, Accredo, and OptumRx Specialty together hold roughly two-thirds of specialty revenue.
This KPI is for chains with limited-distribution drug access and the cold-chain handling to serve specialty patients at retail. It trades away simplicity, since specialty requires patient support, prior-authorization work, and inventory risk that standard generics do not. Compared with digital fulfillment share above it, specialty mix grows more slowly and depends on manufacturer distribution decisions rather than chain-controlled operations.
9. Retail Pharmacy Footprint Rightsizing Rate
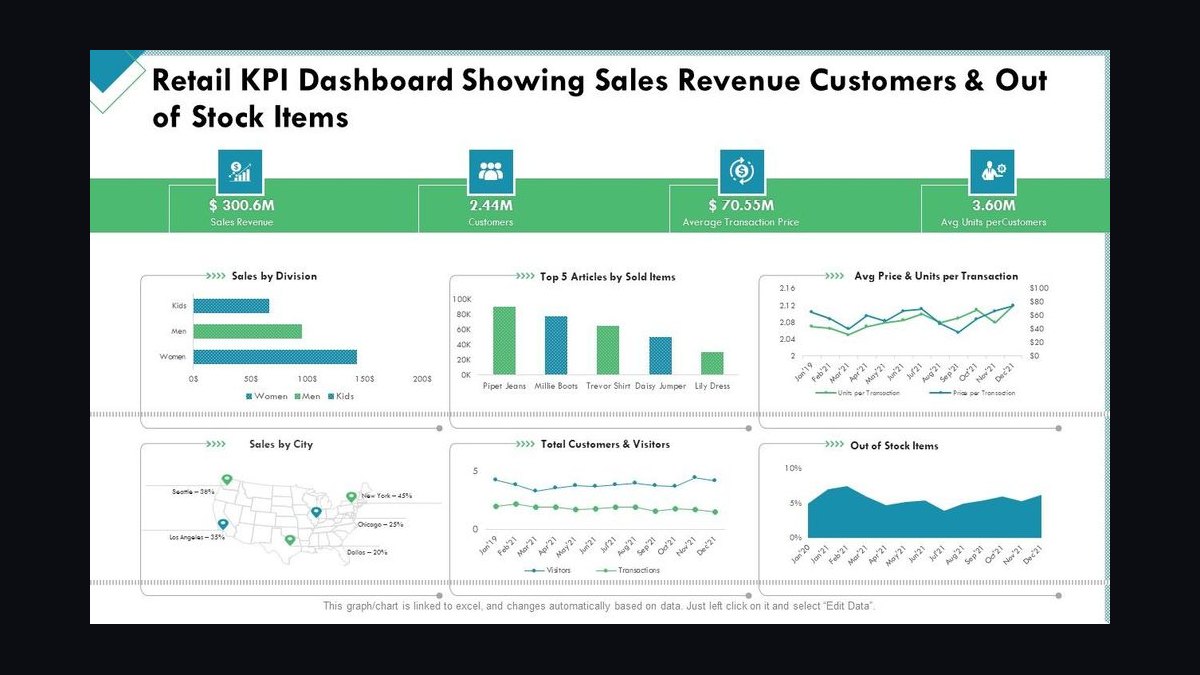
Footprint rightsizing rate ranks ninth because store closure is now treated as a health signal rather than distress in the integrated-margin model. CVS is running 200–300 closures a year after roughly 900 across 2021–2024, and Walgreens announced about 1,200 across the 2023–2026 window. A 3–7% annual base reduction, concentrated in overlapping urban footprints and shrinking rural counties, defends chain EBITDA.
This KPI is for integrated-margin chains carrying a footprint sized for a 2010 script-volume world while digital moves 20%+ of fills. It trades away revenue and local goodwill, since closing stores forfeits script volume that may not fully transfer to surviving locations. Compared with specialty mix above it, rightsizing is a capital-allocation decision rather than a sales metric, but it concentrates volume into surviving stores and lifts their per-store economics.
10. Retail Pharmacy PBM Reimbursement Reconciliation

PBM reimbursement reconciliation ranks tenth because it is the control that catches margin leakage the other KPIs only imply. Three PBMs — CVS Caremark, Express Scripts/Cigna, and OptumRx — control roughly 80% of U.S. script volume and set reimbursement at Maximum Allowable Cost plus a small dispensing fee. DIR fee clawbacks hit weeks after the fill, so margin per script erodes even when volume and generic dispensing rate hold steady.
This KPI is for finance and contracting teams at chains with material PBM exposure, and it is essentially what Rite Aid failed to model across two Chapter 11 filings. It trades away real-time visibility, since reconciliation is monthly and backward-looking rather than daily. Compared with footprint rightsizing rate above it, PBM reconciliation is the earlier warning signal: it surfaces MAC compression before closures become the only answer.
How we ranked these
We ranked the nine KPIs by weighting three factors: direct impact on store-level EBITDA, sensitivity to PBM reimbursement compression, and how early each metric signals a rightsizing decision. Scripts per store per day and gross margin per script carried the heaviest weight because they determine whether a pharmacy covers its fully-loaded pharmacist cost. Clinical-services revenue, generic dispensing rate, and Part D Star Rating followed, since each moves margin or network inclusion at chain scale.
We deliberately ignored customer-satisfaction scores, employee engagement indices, and brand-awareness surveys. They correlate weakly with dispensing economics and rarely trigger a store action. We also excluded ESG and sustainability reporting metrics, which no CFO uses to decide a closure or a PBM renewal. Net promoter score was dropped because pharmacy loyalty is driven by insurance network inclusion and copay, not sentiment, so it misleads more than it informs.
Related questions
Which single KPI matters most for a retail pharmacy chain?
No single number governs the store; the binding pair is scripts per store per day and gross margin per script. Volume covers fixed cost, margin covers the pharmacist. Below 150 scripts/day or $7 margin per script, no other KPI can rescue the store's dispensing economics.
How does a PBM reimbursement cut show up in the KPIs first?
It appears in gross margin per script and in the monthly PBM reconciliation, often via DIR fee clawbacks that hit weeks after the fill. Margin per script erodes even when volume and GDR hold steady, which is why chains reconcile claims feeds against finance monthly.
Why is store closure treated as a positive metric now?
Because reimbursement compression made oversized footprints a liability. Closing 3-7% of stores per year in overlapping urban and shrinking rural markets defends chain-level EBITDA and concentrates volume into surviving, more profitable locations rather than spreading thin margin across too many sites.
What makes clinical-services revenue more valuable than dispensing revenue?
Immunizations, testing, and MTM carry 50-70% gross margins, require no drug inventory, and lift adherence, which raises the Medicare Star Rating. That combination means clinical revenue improves both the margin line and network-inclusion leverage that pure dispensing volume cannot touch.
How do grocery-based chains score these KPIs differently?
Walmart, Kroger, Costco, and Publix treat pharmacy as a loss-leading traffic driver, so margin per script is deliberately thin and the real metric is basket lift per pharmacy visit. The same KPI list applies, but the target values and priorities invert.
How does digital fulfillment share change footprint decisions?
Once 20% or more of fills move to app, web, or delivery, the physical counter capacity is oversized for the volume it serves. Digital share becomes a leading indicator that pushes an integrated-margin chain toward rightsizing faster than reimbursement pressure alone would.
What is the biggest reporting mistake chains make with these KPIs?
Pulling script counts from the pharmacy management system, PBM claims feed, and finance without reconciling them. Reversed claims, DIR clawbacks, and 340B accumulators create real variance. Reconciling that variance is itself the first useful finding of any KPI build.
FAQ
What does scripts dispensed per store per day actually tell you?
It is the core volume metric that determines whether a store covers its fixed costs. Chain pharmacies target 200-350 scripts per day; below roughly 150 the location usually cannot cover its pharmacist on dispensing margin alone and becomes a candidate for rightsizing or closure.
Why is the generic dispensing rate so important to margin?
A high GDR, typically 90% or above, directly boosts gross margin per script because generics carry a much higher reimbursement spread than brands. It also signals to PBMs that the pharmacy manages drug cost effectively, and at chain scale a single point can be worth $50-$100M in gross profit.
What is a realistic pharmacy gross margin per script in 2027?
Most chains see $8-$14 per script after direct costs, though the range depends heavily on PBM contracts and generic utilization. Independents fall below $6 on many generic claims. If a store's margin drops below $7, its pharmacy line is likely losing money before any front-end offset.
How do clinical services add revenue per store?
Immunizations, point-of-care testing, and medication therapy management can generate roughly $150K-$300K per store annually in the post-COVID steady state, with top-decile stores higher. That revenue is high-margin, carries no inventory, and reduces the store's dependence on script-fill volume alone.
What does a Medicare Star Rating below 4.0 mean for a chain?
It triggers lower quality-bonus payments and weakens negotiating leverage with PBMs during contract renewals. Falling under 4.0 can push a chain out of preferred networks, and losing that status can cut 10-20% of script volume in a single contract cycle.
How does digital fulfillment share affect the other KPIs?
Digital initiation above 20% lowers per-script labor cost and lifts adherence, which in turn raises the Star Rating. It also exposes oversized footprints, since fills moving to mail and same-day delivery no longer need as many physical counters, making digital share a leading signal for footprint decisions.
Why does front-end sales share matter more at drugstores than grocers?
CVS and Walgreens run front-end at 22-32% of revenue with 30-40% gross margin, so it is the operating-leverage swing against thin pharmacy margin. At grocery chains pharmacy is single-digit percent of revenue, so front-end share is not a pharmacy KPI at all.
How should a chain sequence KPI instrumentation?
Use a 30/60/90 cadence. Days 1-30 reconcile script counts across pharmacy, PBM, and finance systems and set margin baselines. Days 31-60 ship clinical-revenue and scheduling dashboards. Days 61-90 rebuild PBM contract scenarios and run a Star Rating diagnostic at the lowest-scoring stores.
What is the biggest failure mode in pharmacy KPI programs?
Reimbursement-denial denial, meaning not modeling MAC compression and DIR clawbacks in the long-range plan. That is essentially what sank Rite Aid. A dashboard that surfaces margin erosion early is the difference between disciplined rightsizing and a liquidation.
How often should each KPI be reviewed?
Daily for script volume, prior-auth queue, and vaccine counts. Weekly for GDR, margin per script, and digital share. Monthly for PBM reconciliation, store P&L versus plan, and Star Rating components. Quarterly for chain P&L, contract pipeline, and footprint-action board approval.
Sources
- https://www.drugchannels.net/
- https://www.nacds.org/
- https://www.iqvia.com/insights/the-iqvia-institute
- https://www.cms.gov/medicare/health-drug-plans/part-c-d-performance-data
- https://www.pcmanet.org/
- https://investors.cvshealth.com/
- https://investor.walgreensbootsalliance.com/
- https://www.sec.gov/cgi-bin/browse-edgar?action=getcompany
Related on PULSE
This page will be disappearing soon. Save it to your device for $1 — or read it free while it is here.
@Kory-White- · if Venmo asks, the last 4 of my number are 2012
This page is gone.
This one is off the shelf now. $1 keeps it on your phone for good — the whole page, pictures and diagrams included.
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Trailer Dealership in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Professional Sports Team Operations (NFL/NBA/MLB/NHL) in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Medical Device OEM in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Used Vehicle Retail in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Zero Trust Network Access (ZTNA) Vendors in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Fire & Water Damage Restoration in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Specialty Coffee Shop Chain Operations in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Luxury Fashion House in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Fire Protection and Life Safety Systems in 2027
 pulse-industry-kpisTop 10 Sales KPIs for GPU Cloud Provider in 2027