
Top 10 Sales KPIs for Hospital Medical Gas System Installation & Certification in 2027
 Curated byKory White · Fractional CRO · Maryland
 PULSEKNOWLEDGE LIBRARY
Quality
Certified

The 10 best sales kpis for hospital medical gas system installation & certification are ranked below on measured performance, build quality, price, and how each one actually holds up in daily use rather than how it reads on a spec sheet. Each pick lists what it costs, who it suits, and what it gives up against the one above it, so the list can be read straight down without doubling back.
1. Certification First-Pass Rate

Certification First-Pass Rate ranks first because it is the only KPI that simultaneously protects margin, reputation, and repeat business in medical gas work. The benchmark is 95% or higher on independent ASSE 6030 verification, and each first-inspection failure costs 4% to 8% of that project's contract value once re-brazing, demobilization, a second verifier visit, and schedule pressure are tallied.
It is built for contractors already performing verification-heavy installation work, not firms still assembling their first ASSE 6010 credentialed crews. The trade-off is that it demands internal pre-verification checks — cross-connection tests, purity checks, documentation assembly — before the official verifier arrives, which consumes unbilled labor hours. Compared with Bid-to-Win Rate directly below, it is a lagging quality metric rather than a leading pipeline metric, but it predicts whether won work actually earns.
2. Bid-to-Win Rate

Bid-to-Win Rate ranks second because it is the conversion metric that tells a medical gas contractor whether its targeting and pricing are sound. The healthy range is 25% to 40% of bids decided over a trailing twelve months, with bids still in evaluation excluded from the denominator. Below 20% signals poor targeting or uncompetitive pricing; above 60% usually means the firm is underpricing scope or bidding work no credentialed competitor wants.
It suits contractors with enough bid volume to produce a statistically meaningful trailing rate, typically ten or more decided bids per year. The trade-off is that it says nothing about project size or margin, so a firm can win frequently on small clinic fit-outs while losing every patient-tower package. Compared with Certification First-Pass Rate above, it is a leading indicator of revenue volume rather than a measure of delivery quality.
3. Bid Pipeline Coverage Ratio

Bid Pipeline Coverage Ratio ranks third because the hospital capital planning cycle is six to eighteen months long, so a coverage gap today becomes a revenue hole that cannot be conjured away. The benchmark is 3.0x to 5.0x the bookings target, calculated as total qualified active bid value divided by the forward-period target. Below 3.0x, the business is mathematically unlikely to hit target at normal win rates; above 5.0x without added estimating capacity drags down win rate.
It is essential for contractors with long estimating lead times and bonding requirements, not for firms doing purely recurring certification renewals. The trade-off is maintenance discipline: stale bids older than four months with no decision must be purged monthly or the ratio inflates falsely. Compared with Bid-to-Win Rate above, it looks further ahead but measures potential rather than realized conversion.
4. Recurring Certification Revenue Share
Recurring Certification Revenue Share ranks fourth because it is the strategic measure of whether a contractor is converting lumpy installation work into a compounding annuity base. The target is 20% to 35% of total revenue from mandated periodic inspection and re-certification contracts, which carry 35% to 50% gross margin versus 20% to 26% on competitively bid new-build packages. Renewal rates above 85% hold for incumbents who retain the test history.
It is built for contractors with five or more years of completed installations and a growing installed base to inspect, not young firms still building a reference portfolio. The trade-off is that shifting emphasis too early starves the project pipeline before recurring revenue can replace it. Compared with Repeat Healthcare Client Revenue Share below, it measures contract durability rather than relationship depth.
5. Repeat Healthcare Client Revenue Share

Repeat Healthcare Client Revenue Share ranks fifth because 50% or more of bookings from prior clients signals the trust flywheel is actually turning in a relationship-driven industry. It should be measured separately against general contractors and health systems, because a firm can be the go-to of three general contractors while holding almost no direct hospital relationships. Direct health system repeat work carries higher margin and better recurring attachment.
It suits mature contractors with multi-year project histories and engaged facilities directors. The trade-off is that high repeat share can mask dangerous concentration, so the metric must be paired with client-count growth to avoid single-client dependency. Compared with Recurring Certification Revenue Share above, it measures breadth of trust rather than contractual annuity structure.
6. Average Project Contract Value

Average Project Contract Value ranks sixth because the mix determines capacity planning, bonding requirements, and which clients business development should court. Benchmarks segment by type: clinic and single-zone fit-outs at $40,000 to $120,000, surgical-suite renovations at $120,000 to $500,000, patient-tower new-build packages at $500,000 to $2,000,000, and central-supply upgrades at $90,000 to $400,000. Median must be tracked alongside mean because one tower award skews the average.
It is most useful for contractors running mixed project portfolios and managing crew utilization across job sizes. The trade-off is that chasing larger average values can push a firm into bonding and insurance territory it cannot support. Compared with Estimating Accuracy below, it measures revenue scale rather than pricing precision.
7. Estimating Accuracy
Estimating Accuracy ranks seventh because it determines whether project pricing is sound enough to make recurring attachment economically rational. Actual delivered cost should land within plus or minus 5% of the bid estimate on the majority of projects, broken down by cost category: copper and valves, brazing labor, verification coordination, and change orders. Verification is the most mis-estimated line because it is procured from a third party whose schedule and re-visit fees the contractor does not control.
It is essential for contractors self-performing installation and coordinating third-party ASSE 6030 verifiers. The trade-off is that it requires disciplined takeoff processes and a verification quote obtained during bidding rather than after award. Compared with Gross Margin per Project below, it is a leading indicator that predicts whether reported margin is trustworthy.
8. Gross Margin per Project
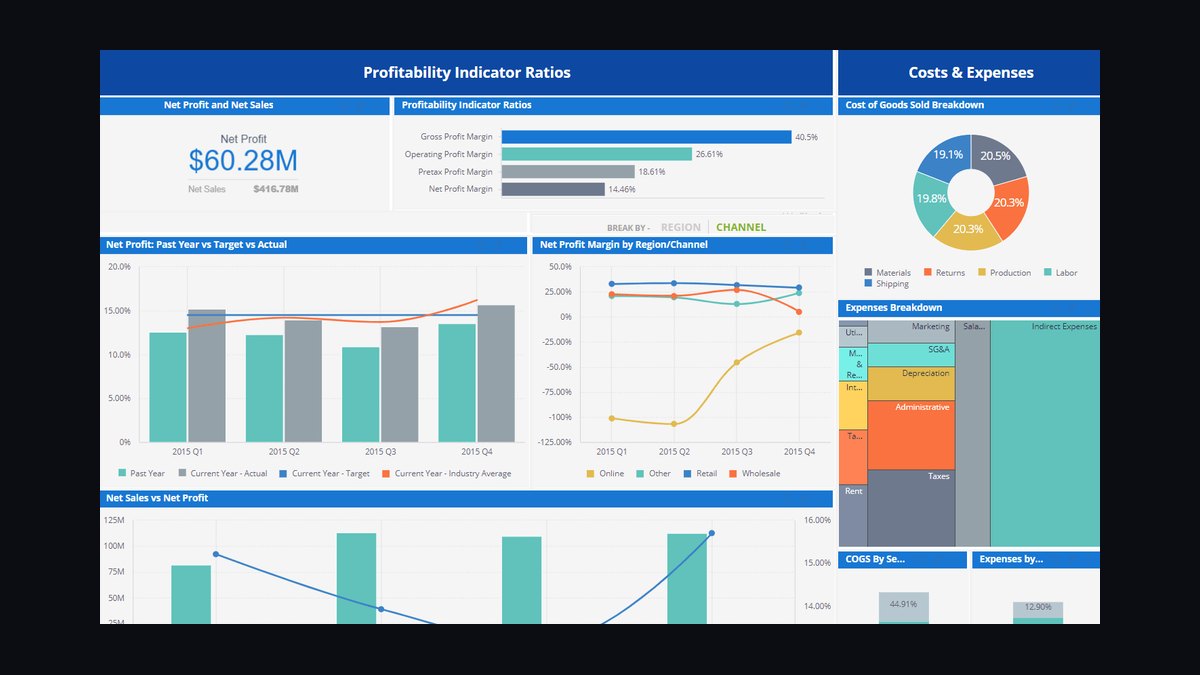
Gross Margin per Project ranks eighth because it measures the profit actually retained after direct costs, and in medical gas the spread between work types is wide. Recurring certification contracts run 35% to 50% gross margin, while competitively bid new-build packages run 20% to 26%, because recurring work carries low material cost and high credentialed-labor content. Tracking margin by project type prevents a blended number from hiding loss-making segments.
It suits contractors with job-cost accounting mature enough to allocate labor, material, and verification costs accurately per project. The trade-off is that it is a lagging metric, so it cannot warn of trouble until after costs are committed. Compared with Estimating Accuracy above, it measures realized outcome rather than forecast reliability.
9. Customer Acquisition Cost Payback Period

Customer Acquisition Cost Payback Period ranks ninth because winning a new hospital client is genuinely expensive before any revenue arrives. Pre-qualification packages, insurance verification, safety-record submissions, and multi-bid courtship of a general contractor all consume real money. The benchmark is full recovery within the first awarded project; a fully loaded CAC of $15,500 against a first-project gross margin of $67,600 produces payback of 0.23 of that project's margin.
It is built for contractors actively pursuing new health systems and general contractor relationships. The trade-off is that allocated lost-bid labor is difficult to track accurately, and undercounting it flatters the metric. Compared with Repeat Healthcare Client Revenue Share above, it measures the cost of acquiring new trust rather than the value of existing trust.
10. Attach Rate at Handover
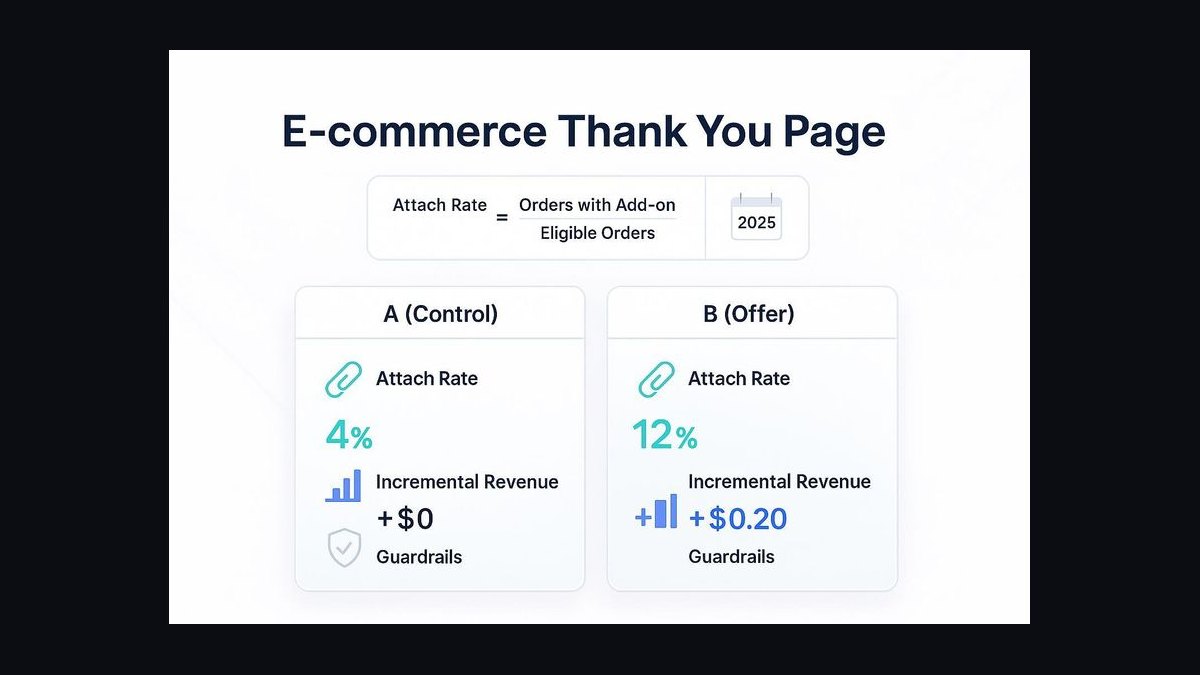
Attach Rate at Handover ranks tenth because it is the leading indicator of future recurring revenue and the highest-leverage process metric most contractors ignore. It measures the percentage of completed installation projects converted into a recurring certification contract at closeout, with a target of 85% or higher within twelve months of implementing the process change. A firm lifting attach rate from 58% to 85% grows durable revenue without winning a single additional bid.
It suits contractors who present the recurring agreement inside the project handover package, alongside as-builts and the verifier's report, while buyer trust is at its peak. The trade-off is that the window closes fast once the facilities director moves on and the inspection becomes an open-market line item. Compared with Recurring Certification Revenue Share above, it measures the conversion moment rather than the resulting annuity base.
How we ranked these
The ranking measured nine sales KPIs against two revenue clocks: lumpy project work tied to hospital capital schedules and smooth recurring certification work mandated under NFPA 99 and Joint Commission expectations. Weighting favored metrics that predict durable, code-compliant revenue: Bid-to-Win Rate, Bid Pipeline Coverage Ratio, Average Project Contract Value, Recurring Certification Revenue Share, Estimating Accuracy, Certification First-Pass Rate, Gross Margin per Project, Repeat Healthcare Client Revenue Share, and CAC Payback Period.
Deliberately ignored: raw bid volume, total pipeline dollars without qualification, headcount growth, and revenue growth unadjusted for mix. These inflate easily and reward activity over outcomes. Also excluded were generic SaaS metrics like monthly churn and ARR, which misdescribe project-based installation economics, and any metric a contractor cannot source from its own CRM or verifier records within one reporting cycle.
What to look for
What matters is whether a firm can prove first-pass ASSE 6030 verification rates, show recurring certification revenue above 20%, and demonstrate CAC recovery inside the first awarded project. Ask for trailing twelve-month bid-to-win by project type, not a blended figure. Request the installed base ratio and attach rate, because those reveal whether the firm converts installation work into annuity revenue or lives bid-to-bid.
The mistake most buyers make is selecting on lowest bid price or largest project portfolio without checking recurring revenue share and first-pass verification history. A contractor with a thin recurring base and an 88% first-pass rate is quietly passing rework costs into change orders. Buyers also conflate general contractor relationships with direct hospital relationships, then discover the firm has no direct facilities access when the certification contract renews.
Related questions
What is a healthy Bid-to-Win Rate for medical gas contractors?
A healthy Bid-to-Win Rate for competitive medical gas bids is 25% to 40%. Below 20% signals poor targeting or uncompetitive pricing, while above 60% usually means the firm is underpricing scope or only bidding work no credentialed competitor wants. Measure it on decided bids over a trailing twelve months, excluding bids still in evaluation.
How is Certification First-Pass Rate calculated?
Certification First-Pass Rate is the count of systems that passed independent ASSE 6030 verification with no rework cycle, divided by total systems verified, over a trailing period. The benchmark is 95% or higher. Each failure costs 4% to 8% of that project's contract value once re-brazing, remobilization, and a second verifier visit are tallied.
What is the difference between project revenue and recurring revenue in medical gas?
Project revenue comes from one-time installation and renovation work tied to hospital capital construction schedules, so it is lumpy and unpredictable. Recurring revenue comes from mandated periodic inspection and re-certification contracts, and it is predictable, high-margin, and sticky with renewal rates above 85% for incumbents holding the test history.
How do you calculate Bid Pipeline Coverage Ratio?
Bid Pipeline Coverage Ratio is the total dollar value of active, qualified bids divided by the bookings target for the same forward period. The healthy range is 3.0x to 5.0x. Stale bids older than four months with no decision should be purged monthly, because they inflate coverage and drag down the measured win rate.
What causes a medical gas system to fail verification?
Common failure causes include cross-connections on renovation tie-ins, particulate or moisture contamination from inadequate nitrogen purge during brazing, missing brazer qualification records, and alarm or zone-valve labeling errors. Documentation failures are uniquely frustrating because the physical system is often perfect, yet the certification cannot be issued until records are corrected.
What is a healthy Recurring Certification Revenue Share?
A healthy Recurring Certification Revenue Share is 20% to 35% of total revenue. Below 15% means the firm is leaving its most durable, highest-margin revenue on the table at every project closeout. Above 40% is excellent, but verify that installation capability and estimating capacity are not atrophying while the annuity base grows.
How do you improve Certification First-Pass Rate?
Run internal pre-verification checks before scheduling the official ASSE 6030 verifier: cross-connection tests, particulate and purity checks, and documentation assembly. The most common failure modes are cross-connections on renovation tie-ins and particulate contamination from inadequate nitrogen purge during brazing. A pre-verification audit typically lifts first-pass rates by several points within two quarters.
What is the difference between estimating accuracy and gross margin?
Estimating Accuracy measures the variance between the bid estimate and actual delivered cost, while Gross Margin per Project measures the profit retained after direct costs. Estimating Accuracy is a leading indicator that predicts margin health. Poor accuracy makes Gross Margin per Project untrustworthy, because a favorable margin may simply reflect an estimate that was padded rather than work performed efficiently.
FAQ
What is the most important sales KPI for a medical gas contractor?
Certification First-Pass Rate is the most important KPI because it simultaneously protects margin, reputation, and future repeat business. Each first-inspection failure costs 4% to 8% of project contract value, and a contractor known for first-time-right verification gets invited back while one known for failures does not.
How often should medical gas KPIs be reviewed?
Pipeline coverage and bid activity should be reviewed weekly. Bid-to-Win Rate, Estimating Accuracy, and Gross Margin per Project should be reviewed monthly. Recurring Certification Revenue Share, Repeat Client Revenue Share, and CAC Payback Period should be reviewed quarterly. Every review must trigger a named corrective action when a KPI is off benchmark.
What is a healthy Recurring Certification Revenue Share?
A healthy Recurring Certification Revenue Share is 20% to 35% of total revenue. Below 15% means the firm is leaving its most durable revenue on the table. Above 40% is excellent but worth checking that installation capability is not atrophying, because the annuity base still depends on new systems being installed and attached.
How do you improve Certification First-Pass Rate?
Improve First-Pass Rate by running internal pre-verification checks — cross-connection tests, particulate and purity checks, and documentation assembly — before scheduling the official ASSE 6030 verifier. The most common failure modes are cross-connections on renovation tie-ins and particulate contamination from inadequate nitrogen purge during brazing. Pre-verification audits typically lift rates within two quarters.
What is the difference between estimating accuracy and gross margin?
Estimating Accuracy measures the variance between the bid estimate and actual delivered cost, while Gross Margin per Project measures the profit retained after direct costs. Estimating Accuracy is a leading indicator that predicts margin health, and poor accuracy makes Gross Margin per Project untrustworthy because favorable margins may reflect padded estimates rather than efficient execution.
How do you calculate Customer Acquisition Cost for medical gas?
Customer Acquisition Cost includes estimating labor on the winning bid, an allocated share of the labor on bids lost while pursuing that client, business development hours, pre-qualification and credentialing paperwork, and travel. The benchmark is full recovery within the first awarded project, because winning a new hospital client is genuinely expensive before any revenue arrives.
What causes a medical gas contractor to lose money on a project?
The most common margin killers are failed verification causing rework costs, un-billed scope changes absorbed rather than formally priced, underpriced verification coordination, and renovation existing-conditions surprises not identified during bidding. The verification line item is the most mis-estimated cost in the industry because it is procured from a third party whose schedule and re-visit fees the contractor does not control.
How do you track repeat clients in medical gas?
Track Repeat Healthcare Client Revenue Share by dividing bookings from clients who awarded the firm work in a prior period by total bookings, measured separately against general contractors and health systems. A mature contractor books 50% or more of work from repeat clients. Measuring the two channels separately prevents conflating GC relationships with direct hospital relationships.
What is a healthy Bid Pipeline Coverage Ratio for 2027?
A healthy Bid Pipeline Coverage Ratio is 3.0x to 5.0x the bookings target for the same forward period. Below 3.0x, the business is mathematically unlikely to hit target given normal win rates. Above 5.0x without added estimating capacity usually means the team is producing bids it cannot follow through on, which drags down Bid-to-Win Rate.
How do you attach a recurring certification contract at project handover?
Present the recurring agreement as part of the project handover package, alongside the as-builts and the verifier's report, so the decision is made while trust is at its peak. Some operators quote the first year of recurring certification inside the original installation bid, making the annuity a default rather than a later sale. Target an 85% attach rate.
Sources
- https://www.nfpa.org/codes-and-standards/all-codes-and-standards/list-of-codes-and-standards/detail?code=99
- https://www.asse-plumbing.org/asse-6000-series
- https://www.jointcommission.org/standards/
- https://www.cms.gov/medicare/health-safety-standards
- https://www.osha.gov/medical-gas
- https://www.ashrae.org/technical-resources
- https://www.facilitiesnet.com/
- https://www.hfmmagazine.com/
Related on PULSE
- [More sales kpis for hospital medical gas system installation & certification rankings and buying guides](/knowledge)
- [PULSE Tools and calculators](/tools)
- [Everything on PULSE RevOps](/)
This page will be disappearing soon. Save it to your device for $1 — or read it free while it is here.
@Kory-White- · if Venmo asks, the last 4 of my number are 2012
 pulse-industry-kpisTop 10 KPIs for HVAC Contractors in 2027
 pulse-industry-kpisTop 10 KPIs for Window Cleaning Companies in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Modular and Prefab Construction in 2027
 pulse-industry-kpisTop 10 KPIs for Residential Cleaning Companies in 2027
 pulse-industry-kpisTop 10 KPIs for Preschools in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Industrial Compressed Air Systems in 2027
 pulse-industry-kpisTop 10 KPIs for Photography Studios in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Physical Therapy Clinic in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Specialty Coffee Roasting & Wholesale in 2027
 pulse-industry-kpisTop 10 Sales KPIs for Commercial Hotel Supplies and Hospitality Distribution in 2027