


How Do I Budget an Optometry Office With an On-Site Lab in 2026?
Quality
Certified
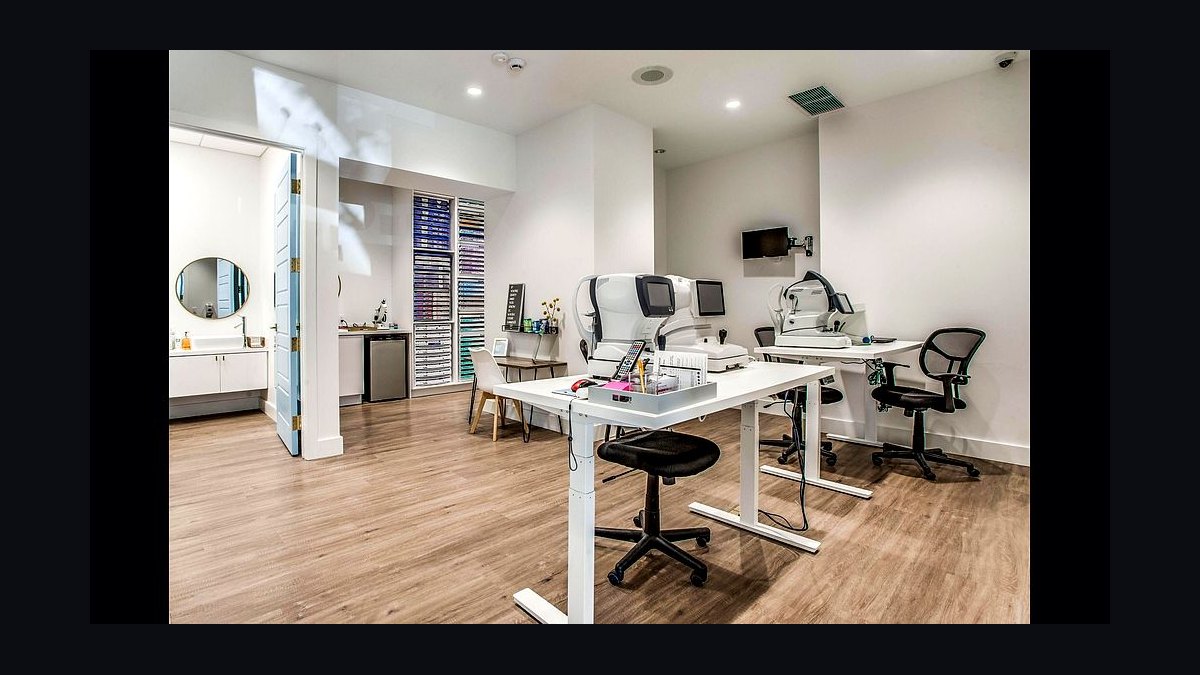
Budget an optometry office with an on-site lab as two businesses under one roof: the exam suite and the finishing lab. For a 1,800–3,000 sq ft Office, plan $120–$250 per sq ft all-in, landing a 2,500 sq ft build around $300,000–$550,000 including equipment. Spend on 2–3 exam lanes and a properly wired edging lab before touching finishes — that combination is what turns the Office into a same-day-glasses competitor instead of a referral pad.
A Concrete Scenario That Frames The Problem
Picture a practice owner who has just signed a letter of intent on a 2,600 sq ft second-generation retail suite. The rent looks reasonable, the location has good foot traffic, and the prior tenant was a dental office, so the owner assumes the electrical and plumbing are "close enough." That assumption is the single most common budgeting mistake in this category. A dental suite's power and drainage layout does not map cleanly onto an optometry Office with an on-site edging lab — the lab needs its own dedicated circuits, often 208–240V at 20–30 amps, plus compressed air or water and a drain that a dental buildout never anticipated.
Six weeks into design, the equipment planner flags that the panel can't support both the diagnostic instruments (auto-refractor, OCT, visual field analyzer) and the edging lab's motor load without a service upgrade. That upgrade — $20,000–$50,000 depending on utility company timelines — wasn't in the original pro forma because the owner budgeted the lab as "$60,000 for equipment" and stopped there. This is the scenario every optometry Budget has to plan around from day one: the lab is not a line item, it's a subsystem with its own electrical, plumbing, ventilation, and staffing requirements that ripple into the lease negotiation, the TI ask, and the equipment financing structure. Getting the sequence right — feasibility study before lease signature, not after — is the difference between a six-month buildout and a fourteen-month one with change orders eating the contingency.

The same scenario plays out with HVAC. Exam lanes need tight temperature and humidity control for instrument calibration, and the lab generates heat from the edger motor and dust from lens grinding. A suite sized for a low-load retail tenant frequently needs added tonnage, which is a mechanical change order most owners don't see coming until the HVAC contractor walks the space with the equipment list in hand.
How The Mechanism Actually Works
The reason an on-site lab changes the entire Budget isn't the equipment cost in isolation — it's that the lab converts a service business into a small manufacturing operation that happens to sit inside a medical retail Office. Every other line item in the buildout gets sized around what the lab requires, not the other way around.

This flow matters because it shows why sequencing beats budgeting in isolation. A practitioner who prices the lab first — before the lease is signed — can use that number to negotiate the landlord's Tenant Improvement allowance upward, because medical-grade electrical, plumbing, and dedicated circuits permanently increase the value of that suite as a medical-use space. Landlords know this, which is why medical TI runs $50–$100 per sq ft versus $20–$40 for a generic retail buildout: they're effectively co-investing in infrastructure they can re-lease to the next medical tenant. An owner who signs the lease first and prices the lab second has already lost that leverage — the TI number is locked before the landlord knows what the lab actually requires.
The mechanism also explains the free-rent ask. Medical permitting — plan review, health department sign-off, inspections tied to plumbing and electrical for the lab — runs slower than a standard retail permit. Six to nine months of free rent isn't a courtesy; it's the realistic gap between lease signature and revenue-generating occupancy once medical permitting and equipment commissioning are accounted for.
Real Numbers, Ranges, And Benchmarks
For a 2,500 sq ft practice running 2–3 exam lanes plus an on-site finishing lab, the全 all-in spend typically breaks down this way:

- Exam lanes (2–3): $70,000–$240,000 total. Each fully equipped lane runs $35,000–$80,000 — chair-and-stand ($8,000–$20,000), phoropter ($3,000–$9,000), slit lamp ($6,000–$15,000), and digital acuity system. The room itself needs dimmable lighting and sound separation, which adds to the construction line rather than the equipment line.
- Pre-test / diagnostic room: $40,000–$150,000. An OCT alone runs $30,000–$80,000; add an auto-refractor, tonometer, and visual field analyzer to round out the range.
- On-site finishing lab: $40,000–$120,000 for the edger, tracer, blocker, lensometer, frame warmer, and tinting station — plus $8,000–$20,000 in supporting infrastructure that's easy to miss: dust collection and ventilation ($3,000–$8,000), compressed air lines ($1,500–$4,000), electrical panel expansion for 208–240V service ($2,000–$6,000), and water filtration/drainage ($1,000–$3,000).
- Lab leasehold improvements versus equipment: split roughly 60/40 in favor of equipment. The physical lab space — reinforced countertops rated for 300–500 lbs, chemical-resistant flooring at $5–$12/sq ft, dedicated plumbing — runs $15,000–$35,000 for a 200–400 sq ft room. The edger, tracer, blocker, and hand tools account for the remaining $40,000–$120,000. Treat these as separate financing instruments: amortize the buildout over the lease term (5–10 years) and lease or finance the equipment separately on a 5–7 year depreciation schedule, because lumping them together distorts both your cash flow planning and your balance sheet.
- Optical dispensary / retail frame display: $25,000–$70,000. This is the highest-margin retail zone in the Office, so it justifies disproportionate finish spend relative to square footage.
- Reception, waiting, contact-lens fitting area: $20,000–$50,000.
- Medical-grade finishes, HVAC zoning, ADA compliance, signage: $40,000–$90,000, with the HVAC number climbing if the lab's heat load requires added tonnage beyond what a standard retail shell provides.
- Staff training and certification: $2,000–$8,000 for lab technician certification (programs like the American Board of Opticianry) plus 40–80 hours of hands-on instruction. If you're training an existing optician rather than hiring lab-experienced talent, budget 1–2 weeks of reduced productivity at roughly $500–$1,000/week in wages against your first-year operating Budget, not your capital Budget.
- Insurance: lab equipment and the associated liability typically raise annual premiums by $1,000–$3,000 — confirm your carrier covers lens-grinding machinery and chemical handling before you finalize numbers.
Add it up and a 2,500 sq ft Office with 2–3 lanes and an on-site lab lands at $300,000–$550,000 all-in. Target occupancy cost — rent plus CAM plus operating expenses tied to the space — under 8–12% of projected collections; above that, the lease is structurally squeezing the practice regardless of how well the buildout itself was priced.

Trade-Offs And Alternatives

The core trade-off in this category is upfront capital versus per-job margin, and it plays out every time a patient walks out with a prescription in hand.
Sending jobs to a wholesale lab instead of building your own gives away $20–$60 per job. At 15–25 jobs per week, an in-house lab can capture $15,000–$70,000 a year that would otherwise go to a third party — but only after the $40,000–$120,000 capital outlay and the ongoing technician labor cost are covered. For a startup practice with thin first-year cash flow, that's a real trade-off: delay the lab and rely on an outside finishing partner for 12–18 months while exam volume builds, or capitalize the lab from day one and accept a longer breakeven on that specific line item in exchange for the same-day-glasses competitive edge from the opening week.
There's a comparable trade-off in equipment condition. Used edgers and blockers from reputable dealers can cut equipment costs 30–50%, which meaningfully changes the capital picture on a $40,000–$120,000 line. The offset is shorter remaining life and a higher chance of repair costs — over a five-year horizon, those can erode some or all of the upfront savings, so this decision should be modeled against your expected patient volume and remake rate, not just the sticker price.

A third alternative worth naming: some practices co-locate or partner with a nearby independent lab rather than building one in-house at all, trading the capital cost and the training burden for a slower turnaround and a permanent per-job fee. That's a legitimate model for a lower-volume practice or a first location where the owner wants to validate exam volume before committing six figures to lab infrastructure — but it forfeits the same-day close that differentiates a brick-and-mortar Optometry practice from online retailers, which is increasingly the competitive question this category has to answer.
Common Pitfalls And How To Avoid Them
The pitfalls in this category cluster around three things: utilities, lease terms, and training — and all three are avoidable with the right sequencing.
Undersized utilities is the classic surprise. The suite's electrical panel or HVAC capacity looks fine for a generic retail tenant and falls short once exam instruments and an edging lab are added to the load. The fix is procedural, not financial: make the lease contingent on a medical-equipment planner's feasibility sign-off before signature, and put base-building electrical and HVAC capacity on the landlord in writing as part of that contingency.

TI held hostage happens when landlords stall the final medical TI draw because medical-grade work is expensive and they want to see it fully complete before releasing funds. Counter this by defining exactly what completes each draw milestone up front and tying releases to third-party inspection sign-offs rather than the landlord's subjective judgment; add a clause letting unpaid TI offset rent if the landlord misses a draw deadline.
Restoration and lab decommissioning clauses can cost $15,000–$40,000 if the lease requires you to rip out the edging lab's plumbing and electrical at term end. Cap restoration at a fixed dollar figure or strike the clause entirely — the argument that medical infrastructure adds value for the next health-care tenant is a reasonable one to make directly to the landlord's broker.
An overly narrow use clause — "optometry only" — can block future revenue lines like dry-eye treatment, aesthetics, or subleasing part of the suite to an ophthalmologist. Broaden it to "eye care and related medical services" at lease signature, when you still have negotiating leverage, not after you've already opened.
No exclusivity clause in a medical building or retail center leaves you exposed to a competing optometrist or optical retailer signing next door. Negotiate an exclusive as part of the same lease package.

Uncapped CAM and à la carte after-hours HVAC billing punishes medical tenants specifically, since Optometry practices often run longer hours than a typical retail neighbor. Cap CAM escalations at roughly 5% per year and negotiate reasonable HVAC operating hours directly into base rent rather than leaving it as a variable charge.
Underbudgeting training is the pitfall that shows up after opening rather than during construction. Skimping on the American Board of Opticianry certification or the 40–80 hours of hands-on lab instruction leads directly to remakes — each costing $15–$40 in materials and 15–30 minutes of technician time — plus the reputational cost of a patient waiting on a redo. Build training into the first-year operating Budget as its own line, not as an afterthought folded into the capital plan.
Applying a RevOps lens to this whole process — treating the lease, the lab, and the staffing plan as one interconnected revenue system rather than three separate procurement decisions — is what keeps the numbers from drifting apart once construction starts.
Related questions
How long does permitting and lab commissioning realistically take?
Plan four to eight months for permitting and buildout, plus two to four weeks for equipment delivery and calibration. Six months from lease signing to opening is a reasonable floor; medical permitting rarely moves faster than that.
How many exam lanes should a practice with an on-site lab plan for?
Most practices function well with three to five lanes: one for pre-testing, two for general exams, and one dedicated to contact lens fittings, while the lab operates independently alongside them.
Should equipment be leased or purchased outright?
Leasing preserves cash for the buildout itself and keeps your Tenant Improvement dollars focused on real estate work; equipment financing is typically structured on a 5–7 year term separate from the lease.
Does an on-site lab affect staffing beyond one technician?
At higher volume, a second trained technician or a rotation with reception staff cross-trained on basic edging tasks prevents the lab from becoming a single point of failure during peak hours.
FAQ
How much does it typically cost to build an on-site edging lab? An on-site edging lab can range from $30,000 to $80,000 for core equipment — the edger, blocker, tracer, and finishing supplies — before installation, ventilation, or electrical upgrades are added.
What's the biggest hidden cost when adding a lab?

Ventilation, electrical, and plumbing modifications often add $5,000 to $15,000 unexpectedly. Labs generate heat and dust, so proper HVAC and dust collection are essential and frequently missing from first-draft budgets.
Can I save money by buying used lab equipment? Yes — used edgers and blockers from reputable dealers can cut equipment costs 30–50%. Weigh that against potential repair costs and shorter remaining life, which can offset the savings over a five-year window.
How many exam lanes should I plan for with a lab? Three to five lanes covers most on-site-lab practices well: one pre-test, two exam, and one contact-lens fitting, with the lab running as a parallel operation rather than competing for the same space.
What's a realistic timeline for lab setup and approval? Permitting and buildout typically take four to eight months, with equipment delivery and calibration adding another two to four weeks — budget at least six months from lease signing to opening day.
Does an on-site lab increase property insurance costs? Yes, typically by $1,000 to $3,000 annually. Confirm with your insurer that the policy covers lens-grinding machinery and potential chemical spills before finalizing the Budget.
Sources
- https://www.cbre.com
- https://www.jll.com
- https://www.cushmanwakefield.com
- https://www.rsmeans.com
- https://www.boma.org
- https://www.aoa.org
- https://www.thevisioncouncil.org
- https://www.iccsafe.org
Related on PULSE
- How do you start an optometry practice in 2027?
- Should I open or buy an Any Lab Test Now franchise in 2027?
- How Many Sales Reps Do I Need to Hire for My Clinical Lab Services Company?
- How Do I Budget a Call Center or BPO Office Buildout?
- How Do I Budget an Orthodontics or Oral-Surgery Office Buildout?
- How Do I Budget a Medical or Dental Office Buildout?
This page will be disappearing soon. Save it to your device for $1 — or read it free while it is here.
@Kory-White- · if Venmo asks, the last 4 of my number are 2012
This page is gone.
This one is off the shelf now. $1 keeps it on your phone for good — the whole page, pictures and diagrams included.
 pulse-qHow Do I Avoid the 'Controllable vs Uncontrollable' CAM Trap in 2026?
 pulse-qHow do you coach a veteran rep who's coasting in 2026?
 pulse-qHow Do I Budget a Med Spa Buildout in 2026?
 pulse-qHow Do I Get Out of a Commercial Lease Early Without Paying a Fortune in 2026?
 pulse-qShould I open a gutter cleaning business in 2027?
 pulse-qHow do you certify sales skills before reps face real buyers in 2026?
 pulse-qShould I open or buy an Ideal Image franchise in 2027?
 pulse-qShould I open or buy a Sky Zone trampoline park franchise in 2027?
 pulse-qShould I open or buy an IHOP franchise in 2027?
 pulse-qHow Many Employees Should I Schedule Each Shift at My Language School in 2026?